04.02.02.HER.20241010.01 — Formulario para Trámites de Modificaciones Posteriores al Registro de Dispositivos Médicos
Currentness under review. Whether this instrument remains applicable is under review. Consult the later instruments and source context below before relying on it.
Link directly to a passage with its anchor — for example #office-render-page-1 — to open it highlighted. This reference version is generated from the authority’s publication and does not replace it. Language: Spanish.
GOBIERNO DE EL SALVADOR
SUPERINTENDENCIA DE REGULACIÓN SANITARIA
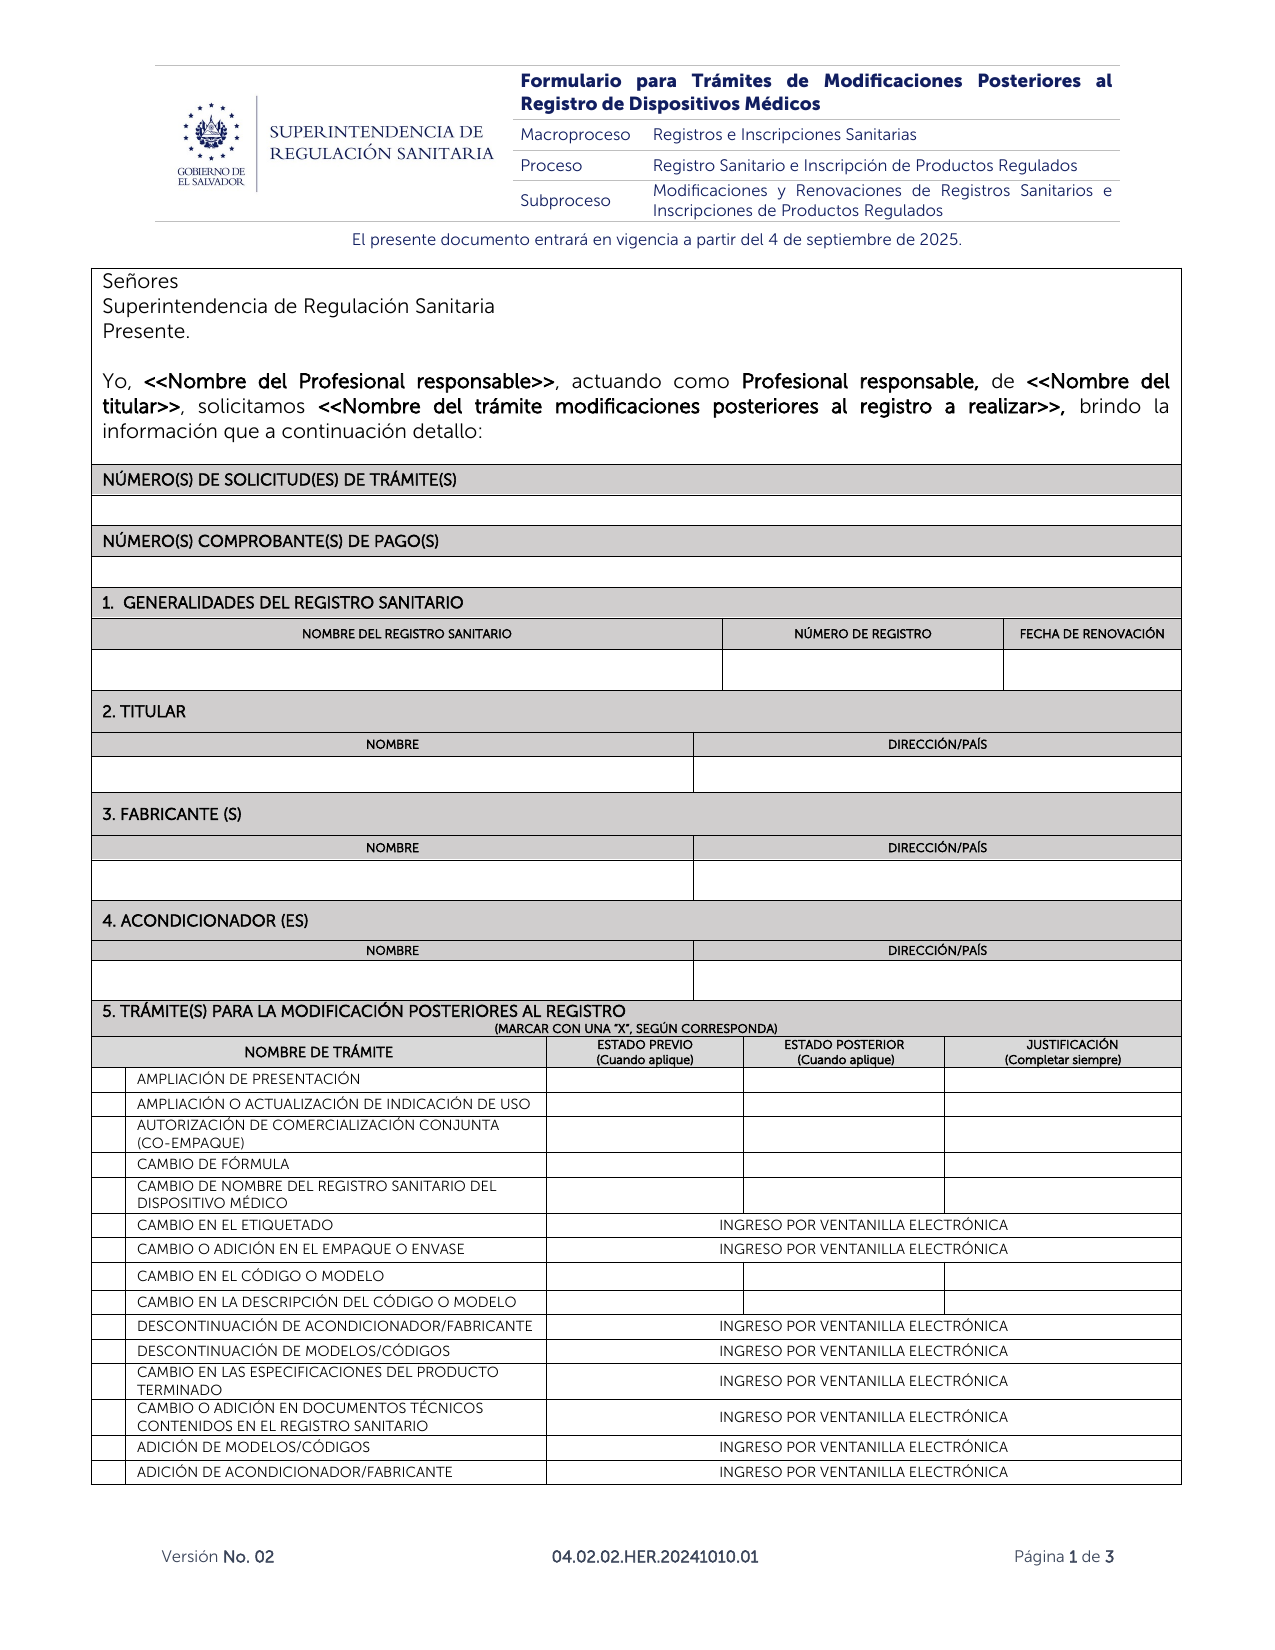
Formulario para Trámites de Modificaciones Posteriores al
Registro de Dispositivos Médicos
Macroproceso Registros e Inscripciones Sanitarias
Proceso Registro Sanitario e Inscripción de Productos Regulados
Subproceso Modificaciones y Renovaciones de Registros Sanitarios e
Inscripciones de Productos Regulados
Señores
Superintendencia de Regulación Sanitaria
Presente.
Yo, <<Nombre del Profesional responsable>>, actuando como Profesional responsable, de <<Nombre del
titular>>, solicitamos <<Nombre del trámite modificaciones posteriores al registro a realizar>>, brindo la
información que a continuación detallo:
NÚMERO(S) DE SOLICITUD(ES) DE TRÁMITE(S)
NÚMERO(S) COMPROBANTE(S) DE PAGO(S)
1. GENERALIDADES DEL REGISTRO SANITARIO
NOMBRE DEL REGISTRO SANITARIO NÚMERO DE REGISTRO FECHA DE RENOVACIÓN
2. TITULAR
NOMBRE DIRECCIÓN/PAÍS
3. FABRICANTE (S)
NOMBRE DIRECCIÓN/PAÍS
4. ACONDICIONADOR (ES)
NOMBRE DIRECCIÓN/PAÍS
5. TRÁMITE(S) PARA LA MODIFICACIÓN POSTERIORES AL REGISTRO
(MARCAR CON UNA “X”, SEGÚN CORRESPONDA)
NOMBRE DE TRÁMITE ESTADO PREVIO
(Cuando aplique)
ESTADO POSTERIOR
(Cuando aplique)
JUSTIFICACIÓN
(Completar siempre)
AMPLIACIÓN DE PRESENTACIÓN
AMPLIACIÓN O ACTUALIZACIÓN DE INDICACIÓN DE USO
AUTORIZACIÓN DE COMERCIALIZACIÓN CONJUNTA
(CO-EMPAQUE)
CAMBIO DE FÓRMULA
CAMBIO DE NOMBRE DEL REGISTRO SANITARIO DEL
DISPOSITIVO MÉDICO
CAMBIO EN EL ETIQUETADO INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO O ADICIÓN EN EL EMPAQUE O ENVASE INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO EN EL CÓDIGO O MODELO
CAMBIO EN LA DESCRIPCIÓN DEL CÓDIGO O MODELO
DESCONTINUACIÓN DE ACONDICIONADOR/FABRICANTE INGRESO POR VENTANILLA ELECTRÓNICA
DESCONTINUACIÓN DE MODELOS/CÓDIGOS INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO EN LAS ESPECIFICACIONES DEL PRODUCTO
TERMINADO INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO O ADICIÓN EN DOCUMENTOS TÉCNICOS
CONTENIDOS EN EL REGISTRO SANITARIO INGRESO POR VENTANILLA ELECTRÓNICA
ADICIÓN DE MODELOS/CÓDIGOS INGRESO POR VENTANILLA ELECTRÓNICA
ADICIÓN DE ACONDICIONADOR/FABRICANTE INGRESO POR VENTANILLA ELECTRÓNICA
El presente documento entrará en vigencia a partir del 4 de septiembre de 2025.
Versión No. 02
04.02.02.HER.20241010.01
Página 1 de 3
Rendered from the linked Office original — page 1; retained table layout and symbols. This is a render, not an official PDF page.
GOBIERNO DE EL SALVADOR
SUPERINTENDENCIA DE REGULACIÓN SANITARIA
Formulario para Trámites de Modificaciones Posteriores al
Registro de Dispositivos Médicos
Macroproceso Registros e Inscripciones Sanitarias
Proceso Registro Sanitario e Inscripción de Productos Regulados
Subproceso Modificaciones y Renovaciones de Registros Sanitarios e
Inscripciones de Productos Regulados
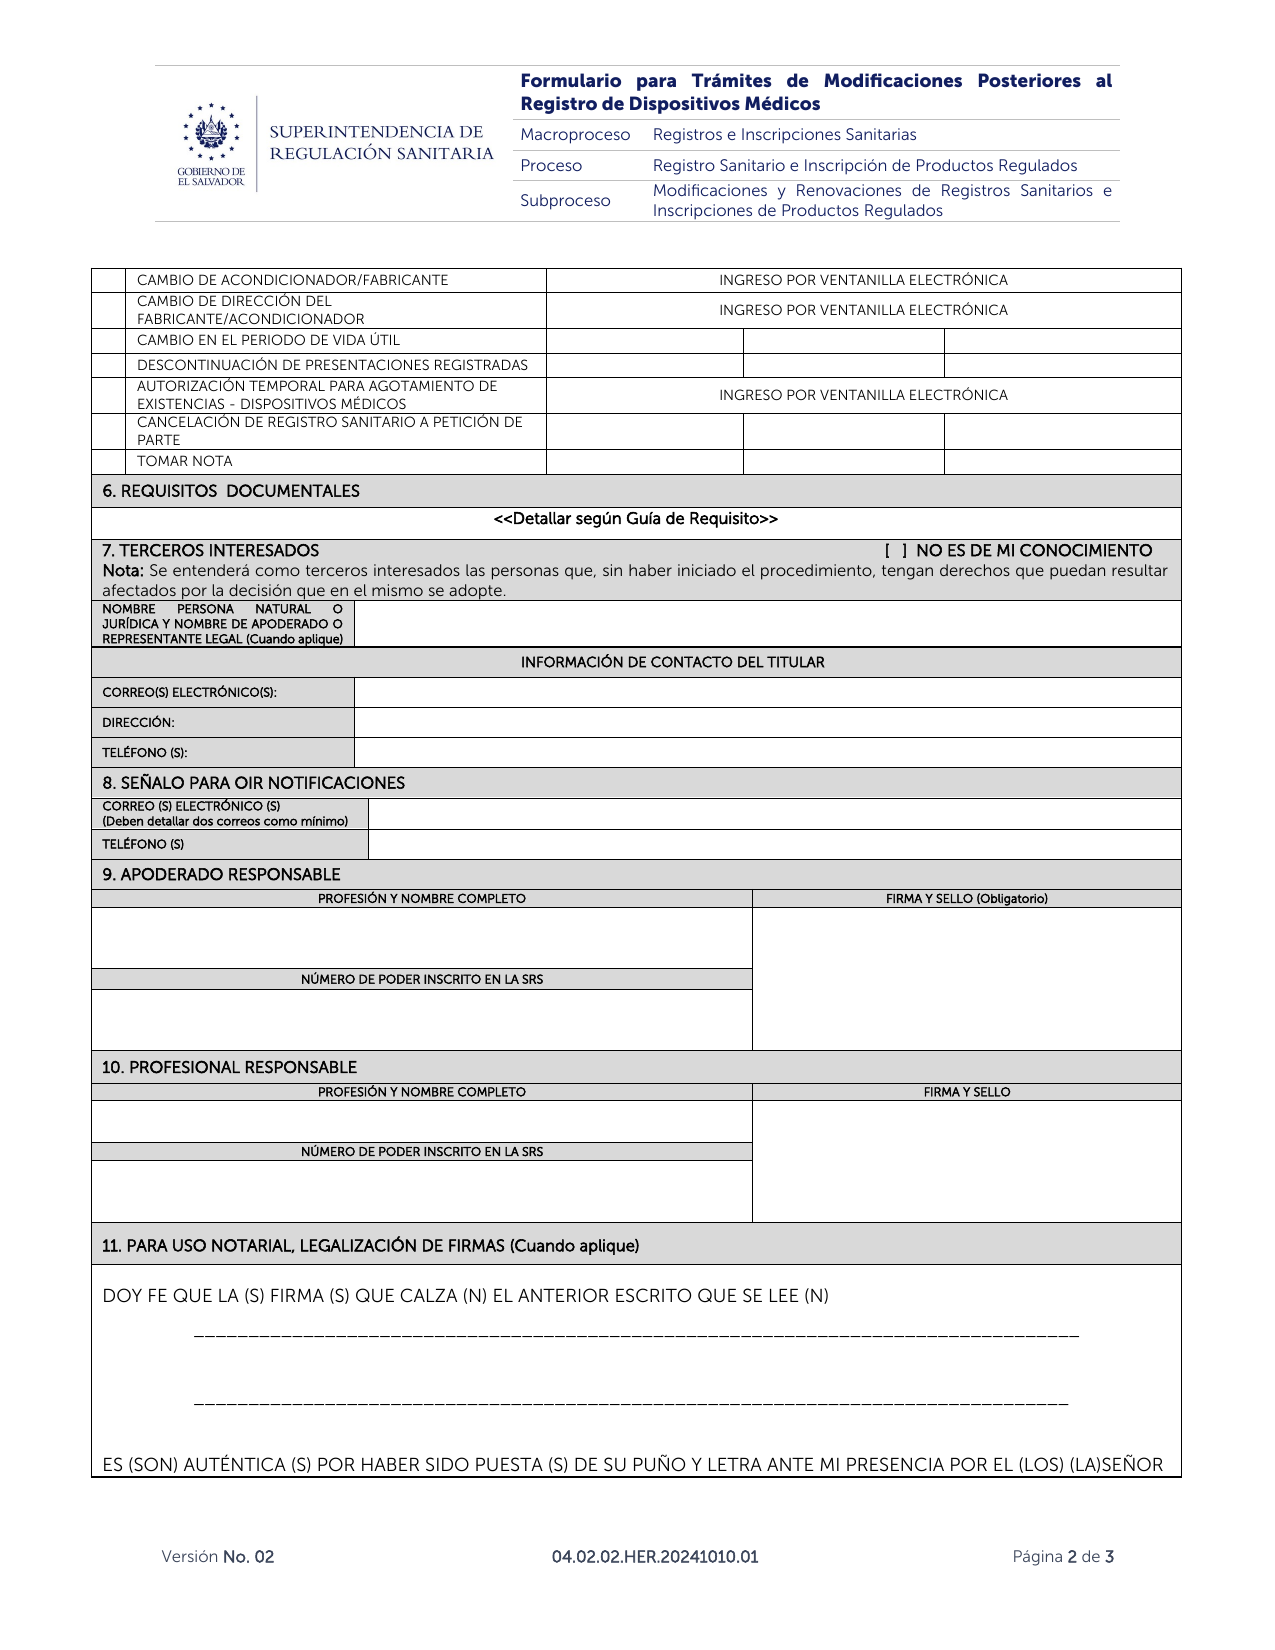
CAMBIO DE ACONDICIONADOR/FABRICANTE INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO DE DIRECCIÓN DEL
FABRICANTE/ACONDICIONADOR INGRESO POR VENTANILLA ELECTRÓNICA
CAMBIO EN EL PERIODO DE VIDA ÚTIL
DESCONTINUACIÓN DE PRESENTACIONES REGISTRADAS
AUTORIZACIÓN TEMPORAL PARA AGOTAMIENTO DE
EXISTENCIAS - DISPOSITIVOS MÉDICOS INGRESO POR VENTANILLA ELECTRÓNICA
CANCELACIÓN DE REGISTRO SANITARIO A PETICIÓN DE
PARTE
TOMAR NOTA
6. REQUISITOS DOCUMENTALES
<<Detallar según Guía de Requisito>>
7. TERCEROS INTERESADOS [ ] NO ES DE MI CONOCIMIENTO
Nota: Se entenderá como terceros interesados las personas que, sin haber iniciado el procedimiento, tengan derechos que puedan resultar
afectados por la decisión que en el mismo se adopte.
NOMBRE PERSONA NATURAL O
JURÍDICA Y NOMBRE DE APODERADO O
REPRESENTANTE LEGAL (Cuando aplique)
INFORMACIÓN DE CONTACTO DEL TITULAR
CORREO(S) ELECTRÓNICO(S):
DIRECCIÓN:
TELÉFONO (S):
8. SEÑALO PARA OIR NOTIFICACIONES
CORREO (S) ELECTRÓNICO (S)
(Deben detallar dos correos como mínimo)
TELÉFONO (S)
9. APODERADO RESPONSABLE
PROFESIÓN Y NOMBRE COMPLETO FIRMA Y SELLO (Obligatorio)
NÚMERO DE PODER INSCRITO EN LA SRS
10. PROFESIONAL RESPONSABLE
PROFESIÓN Y NOMBRE COMPLETO FIRMA Y SELLO
NÚMERO DE PODER INSCRITO EN LA SRS
11. PARA USO NOTARIAL, LEGALIZACIÓN DE FIRMAS (Cuando aplique)
DOY FE QUE LA (S) FIRMA (S) QUE CALZA (N) EL ANTERIOR ESCRITO QUE SE LEE (N)
__________________________________________________________________________________-
________________________________________________________________________________-
-
ES (SON) AUTÉNTICA (S) POR HABER SIDO PUESTA (S) DE SU PUÑO Y LETRA ANTE MI PRESENCIA POR EL (LOS) (LA)SEÑOR
Versión No. 02
04.02.02.HER.20241010.01
Página 2 de 3
Rendered from the linked Office original — page 2; retained table layout and symbols. This is a render, not an official PDF page.
GOBIERNO DE EL SALVADOR
SUPERINTENDENCIA DE REGULACIÓN SANITARIA
Formulario para Trámites de Modificaciones Posteriores al
Registro de Dispositivos Médicos
Macroproceso Registros e Inscripciones Sanitarias
Proceso Registro Sanitario e Inscripción de Productos Regulados
Subproceso Modificaciones y Renovaciones de Registros Sanitarios e
Inscripciones de Productos Regulados
(A)(ES)
- -
Nombre del apoderado responsable
- -
Nombre del profesional responsable
DE ________________________________________AÑOS DE EDAD (RESPECTIVAMENTE), DEL DOMICILIO DE
_____________________________________________________________A QUIEN (ES) CONOZCO POR SU (S)
______________________ NÚMERO (S) - (RESPECTIVAMENTE), (CIUDAD O DEPARTAMENTO) A LOS
_________________________________________________________________________________________________
_________________________________________________________________________________________________
_________________________________________________
Firma y sello del Notario
Notas:
1. La presente no tiene validez sin el nombre y la firma exigidos.
2. Los documentos ingresados y en trámite no serán devueltos.
3. Las traducciones deben hacerse de forma íntegra vertiendo al castellano todo lo que se encuentre en idioma extranjero.
Según art. 62 de la Constitución de la República y el Art. 103 del Reglamento General de la Ley de Medicamentos.
Versión No. 02
04.02.02.HER.20241010.01
Página 3 de 3
Rendered from the linked Office original — page 3; retained table layout and symbols. This is a render, not an official PDF page.