MCA-F-501/01, version 2 – 24 January 2025 — Clinical Trial Application Form
Currentness under review. Whether this instrument remains applicable is under review. Consult the later instruments and source context below before relying on it.
Link directly to a passage with its anchor — for example #pdf-page-1 — to open it highlighted. This reference version is generated from the authority’s publication and does not replace it. Language: English.
Contents
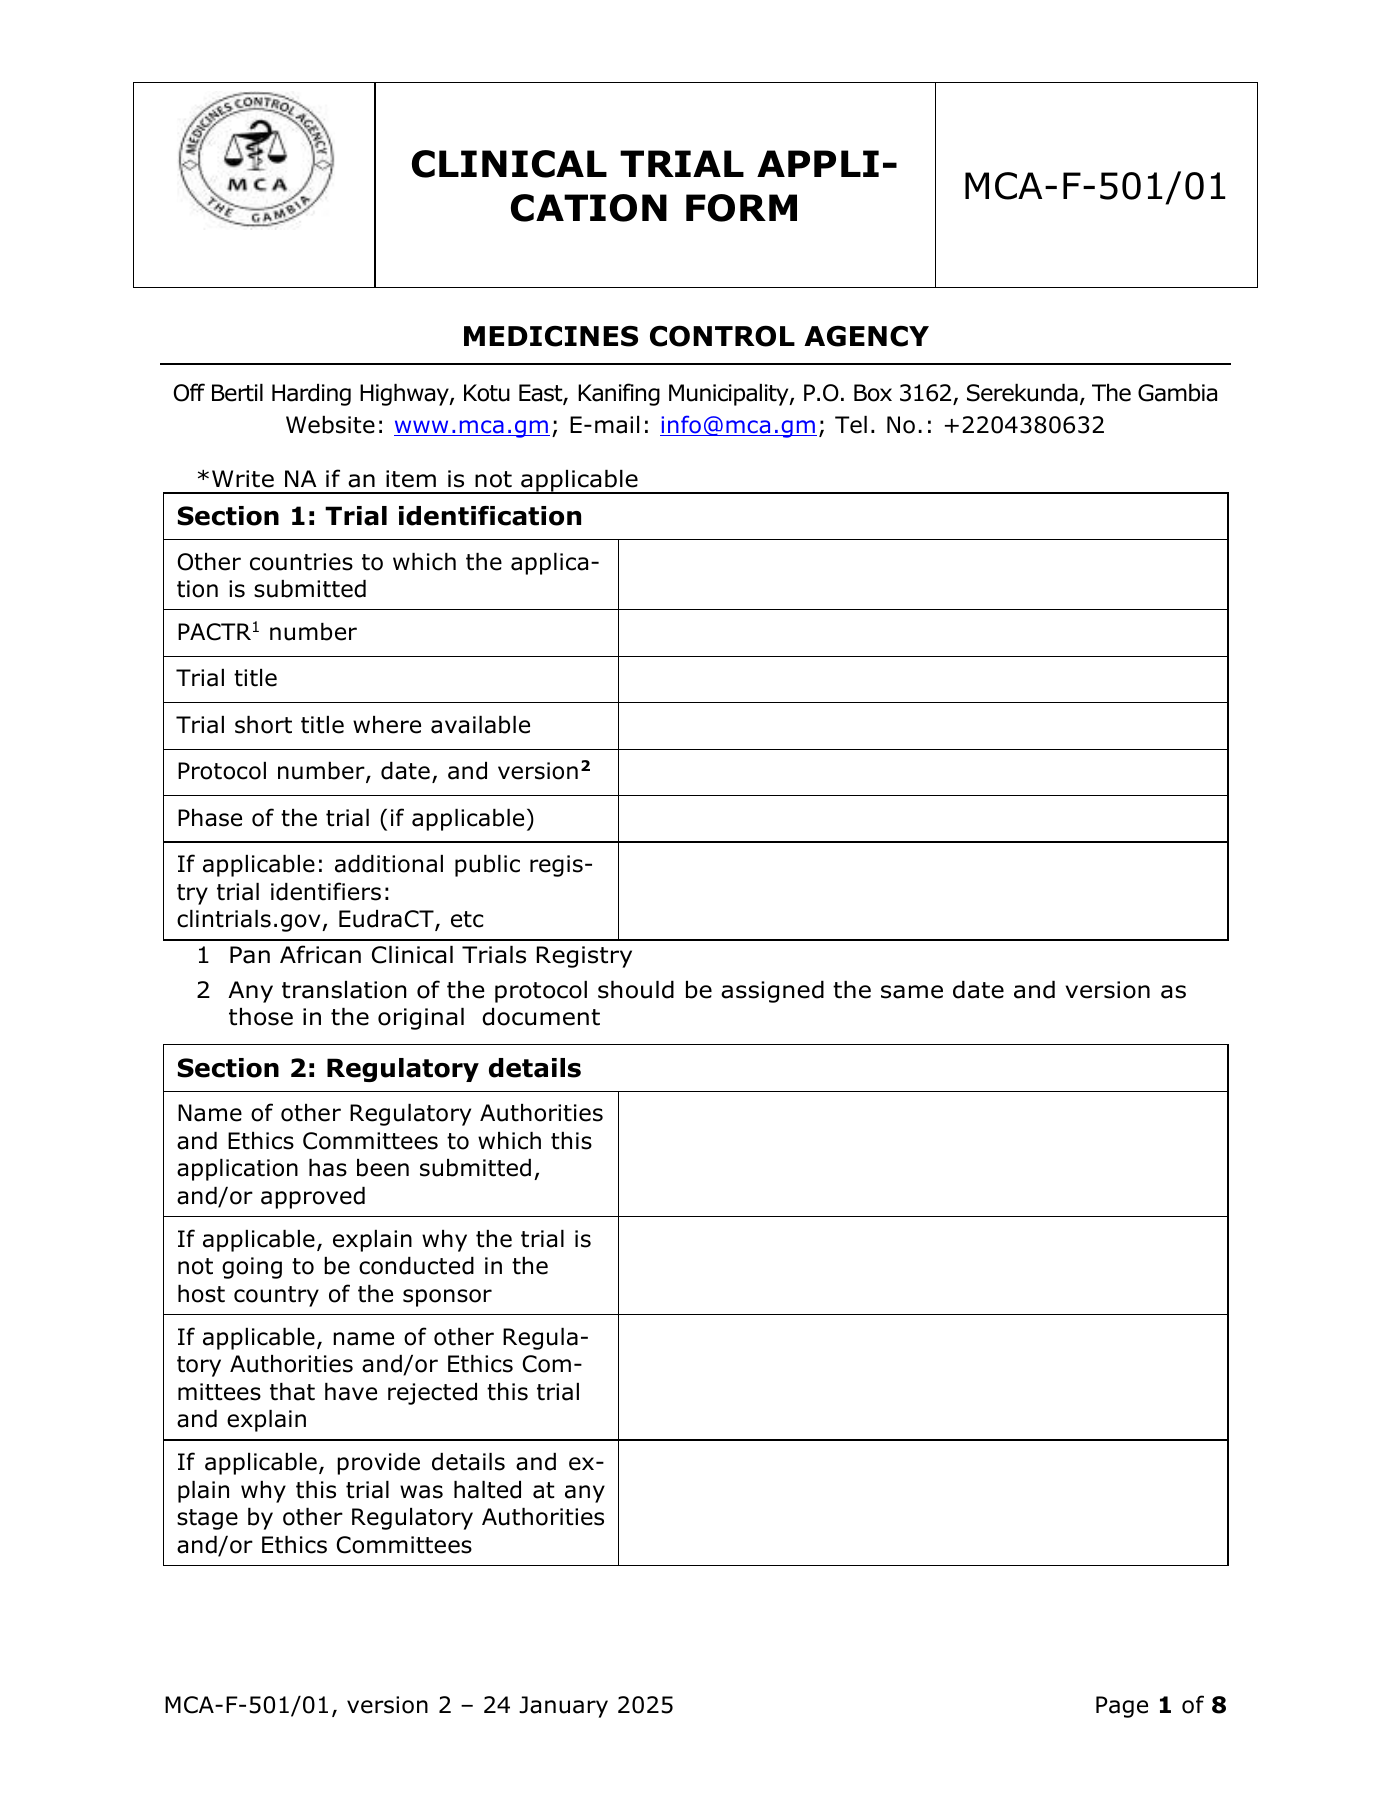
MEDICINES CONTROL AGENCY
MCA
THE GAMBIA
CLINICAL TRIAL APPLI-
MCA-F-501/01
CATION FORM
MEDICINES CONTROL AGENCY
Off Bertil Harding Highway, Kotu East, Kanifing Municipality, P.O. Box 3162, Serekunda, The Gambia
Website: www.mca.gm; E-mail: info@mca.gm; Tel. No.: +2204380632
*Write NA if an item is not applicable
Section 1: Trial identification
Other countries to which the applica-
tion is submitted
PACTR1 number
Trial title
Trial short title where available
Protocol number, date, and version2
Phase of the trial (if applicable)
If applicable: additional public regis-
try trial identifiers:
clintrials.gov, EudraCT, etc
1 Pan African Clinical Trials Registry
2 Any translation of the protocol should be assigned the same date and version as
those in the original document
Section 2: Regulatory details
Name of other Regulatory Authorities
and Ethics Committees to which this
application has been submitted,
and/or approved
If applicable, explain why the trial is
not going to be conducted in the
host country of the sponsor
If applicable, name of other Regula-
tory Authorities and/or Ethics Com-
mittees that have rejected this trial
and explain
If applicable, provide details and ex-
plain why this trial was halted at any
stage by other Regulatory Authorities
and/or Ethics Committees
MCA-F-501/01, version 2 – 24 January 2025 Page 1 of 8
Original PDF page 1 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
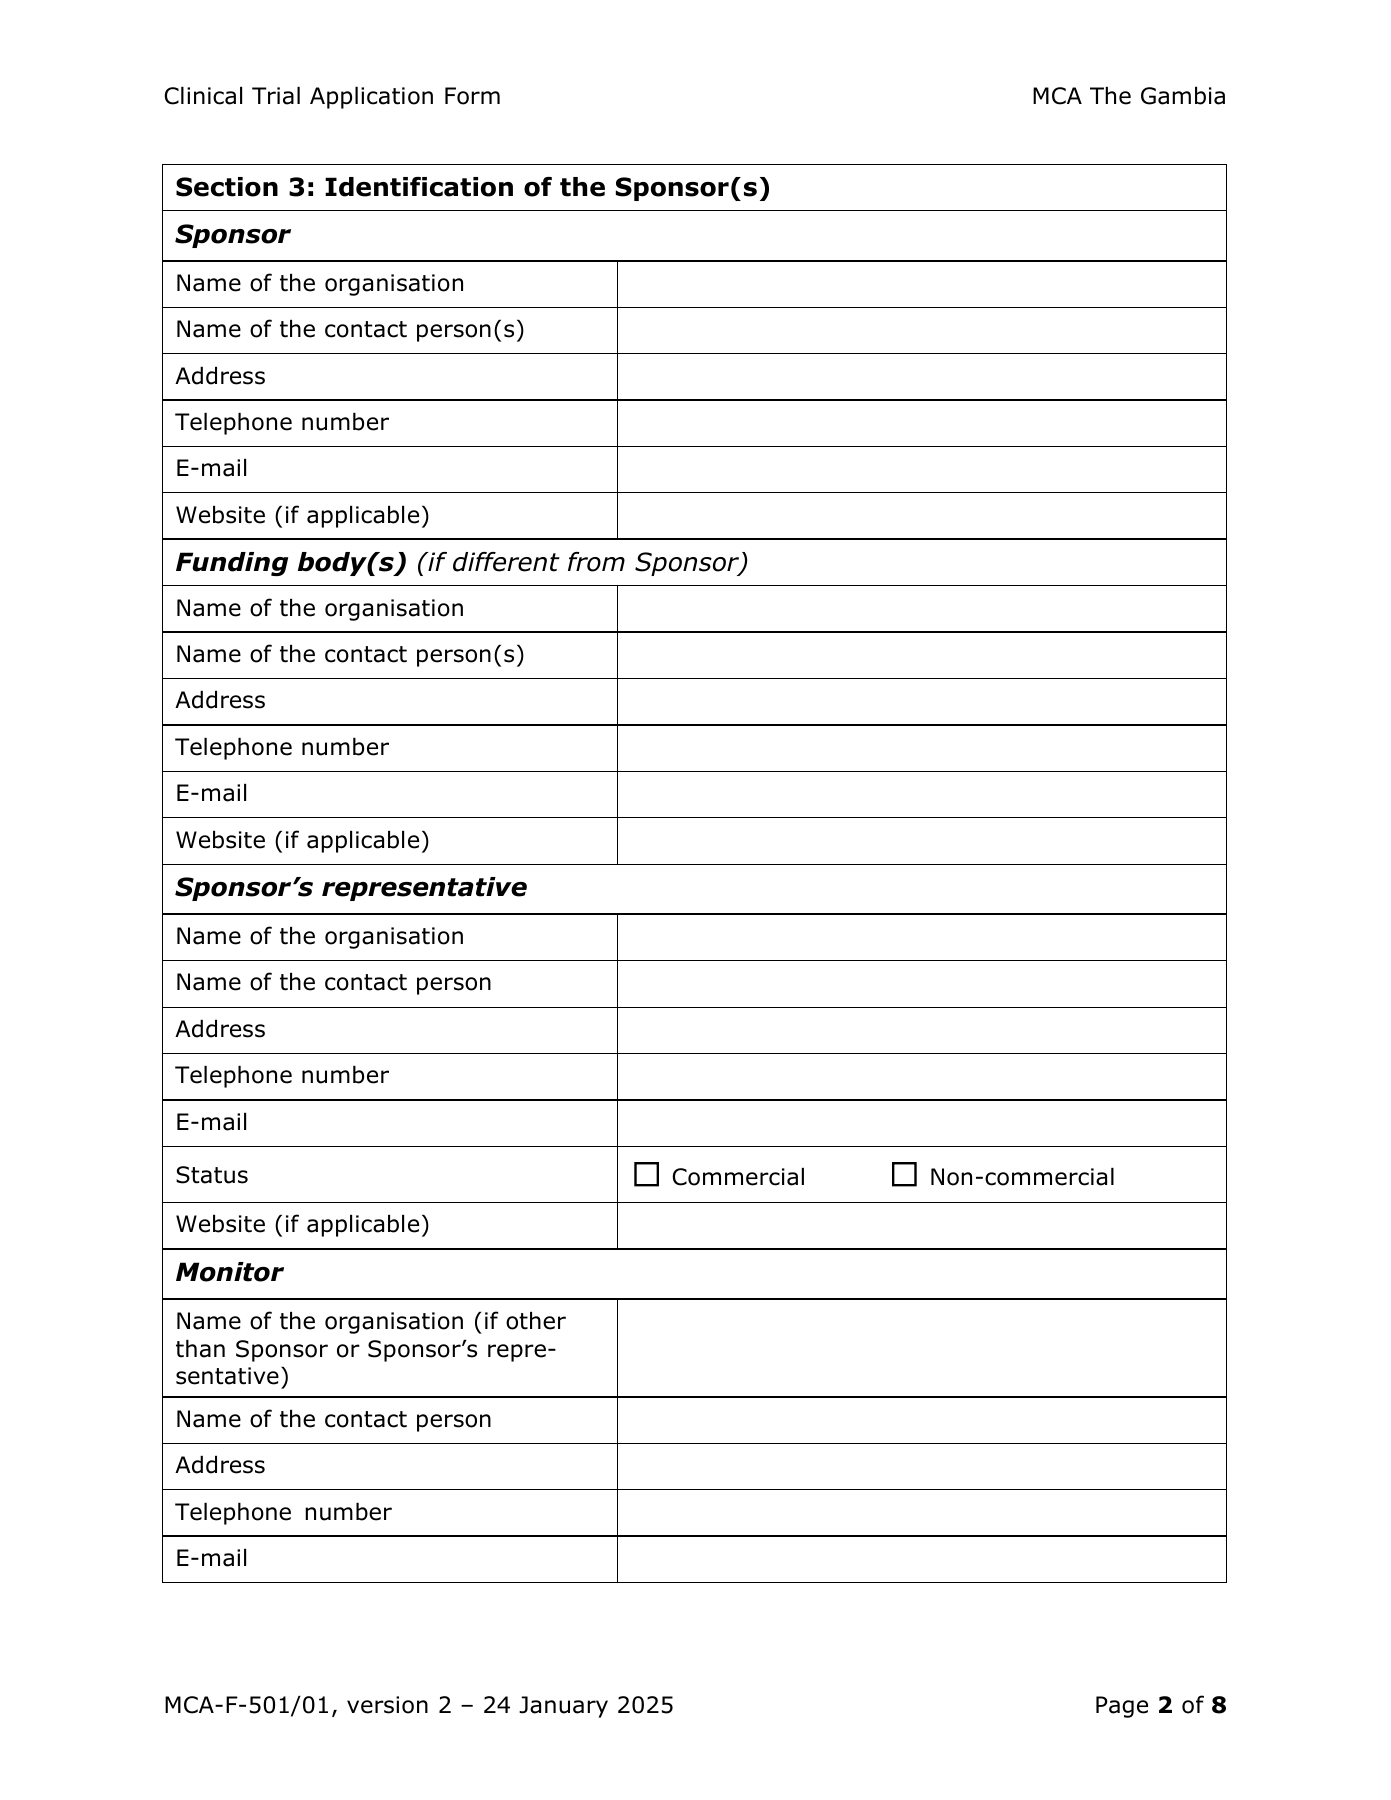
Section 3: Identification of the Sponsor(s)
Sponsor
Name of the organisation
Name of the contact person(s)
Address
Telephone number
E-mail
Website (if applicable)
Funding body(s) (if different from Sponsor)
Name of the organisation
Name of the contact person(s)
Address
Telephone number
E-mail
Website (if applicable)
Sponsor’s representative
Name of the organisation
Name of the contact person
Address
Telephone number
E-mail
Status ☐ Commercial ☐ Non-commercial
Website (if applicable)
Monitor
Name of the organisation (if other
than Sponsor or Sponsor’s repre-
sentative)
Name of the contact person
Address
Telephone number
E-mail
MCA-F-501/01, version 2 – 24 January 2025 Page 2 of 8
Original PDF page 2 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
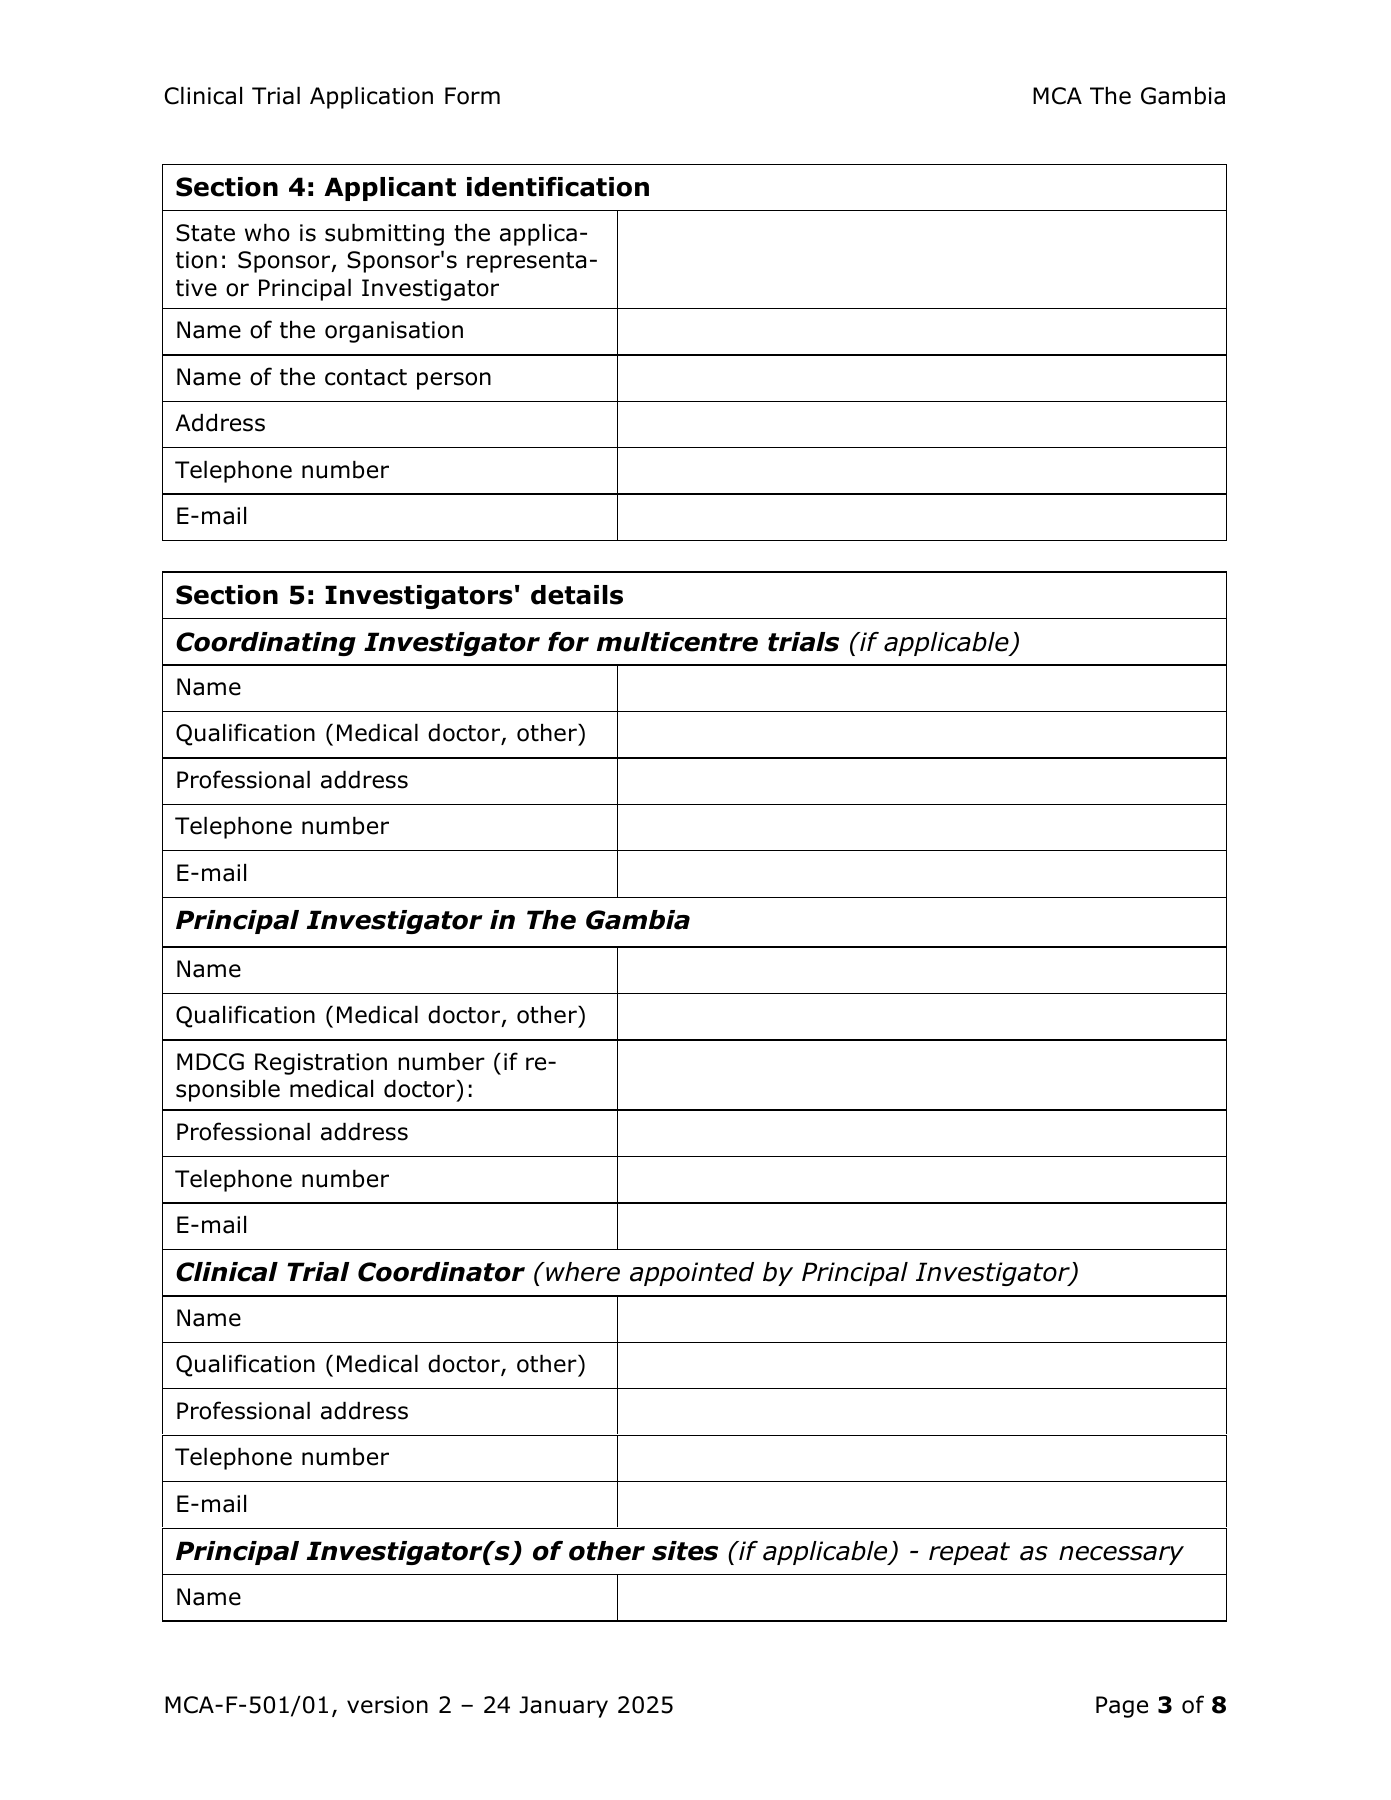
Section 4: Applicant identification
State who is submitting the applica-
tion: Sponsor, Sponsor's representa-
tive or Principal Investigator
Name of the organisation
Name of the contact person
Address
Telephone number
E-mail
Section 5: Investigators' details
Coordinating Investigator for multicentre trials (if applicable)
Name
Qualification (Medical doctor, other)
Professional address
Telephone number
E-mail
Principal Investigator in The Gambia
Name
Qualification (Medical doctor, other)
MDCG Registration number (if re-
sponsible medical doctor):
Professional address
Telephone number
E-mail
Clinical Trial Coordinator (where appointed by Principal Investigator)
Name
Qualification (Medical doctor, other)
Professional address
Telephone number
E-mail
Principal Investigator(s) of other sites (if applicable) - repeat as necessary
Name
MCA-F-501/01, version 2 – 24 January 2025 Page 3 of 8
Original PDF page 3 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
Qualification (Medical doctor, other)
Professional address
Telephone number
E-mail
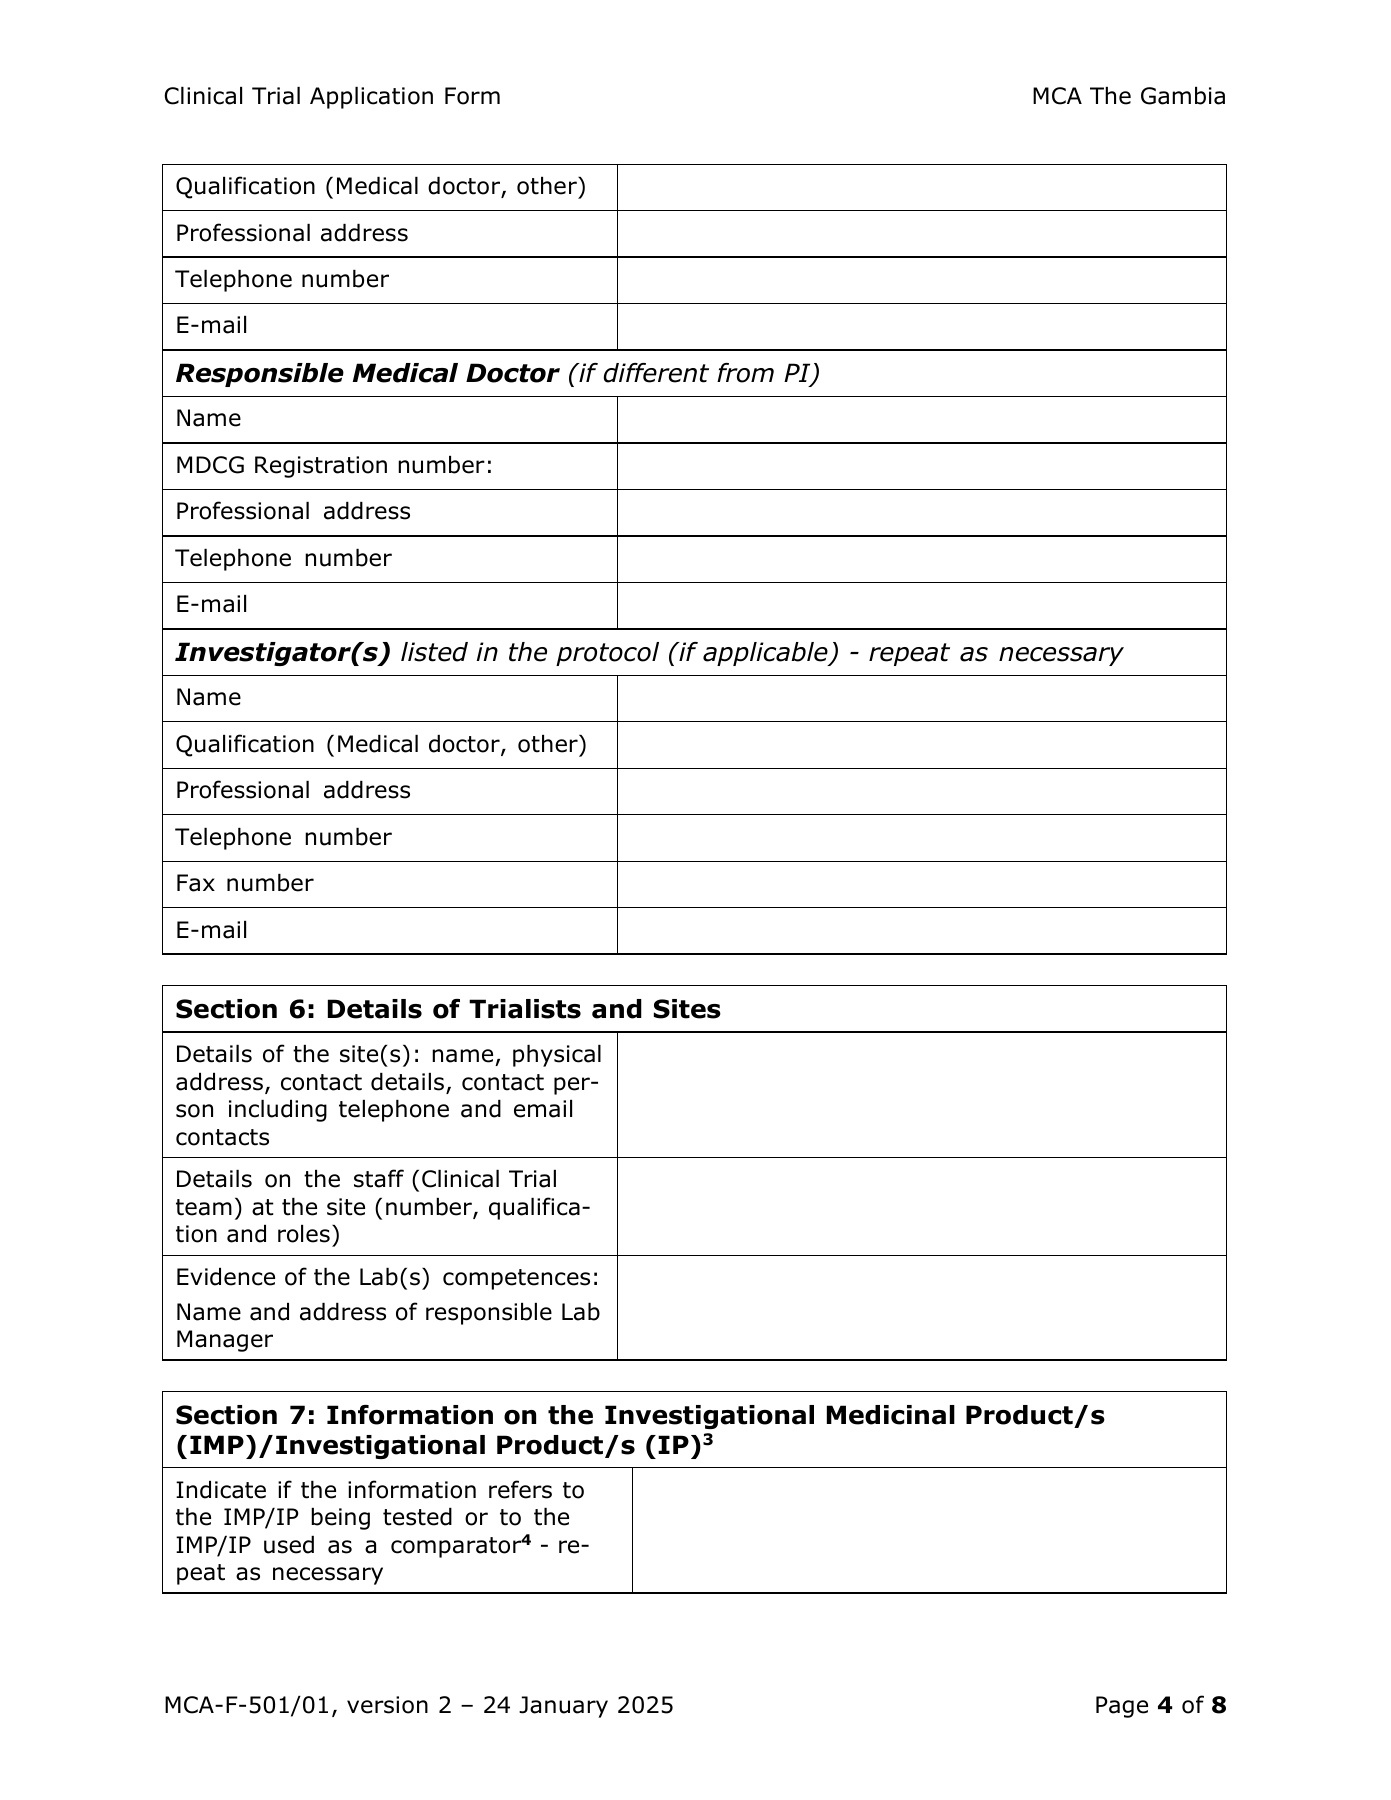
Responsible Medical Doctor (if different from PI)
Name
MDCG Registration number:
Professional address
Telephone number
E-mail
Investigator(s) listed in the protocol (if applicable) - repeat as necessary
Name
Qualification (Medical doctor, other)
Professional address
Telephone number
Fax number
E-mail
Section 6: Details of Trialists and Sites
Details of the site(s): name, physical
address, contact details, contact per-
son including telephone and email
contacts
Details on the staff (Clinical Trial
team) at the site (number, qualifica-
tion and roles)
Evidence of the Lab(s) competences:
Name and address of responsible Lab
Manager
Section 7: Information on the Investigational Medicinal Product/s
(IMP)/Investigational Product/s (IP)3
Indicate if the information refers to
the IMP/IP being tested or to the
IMP/IP used as a comparator4 - re-
peat as necessary
MCA-F-501/01, version 2 – 24 January 2025 Page 4 of 8
Original PDF page 4 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
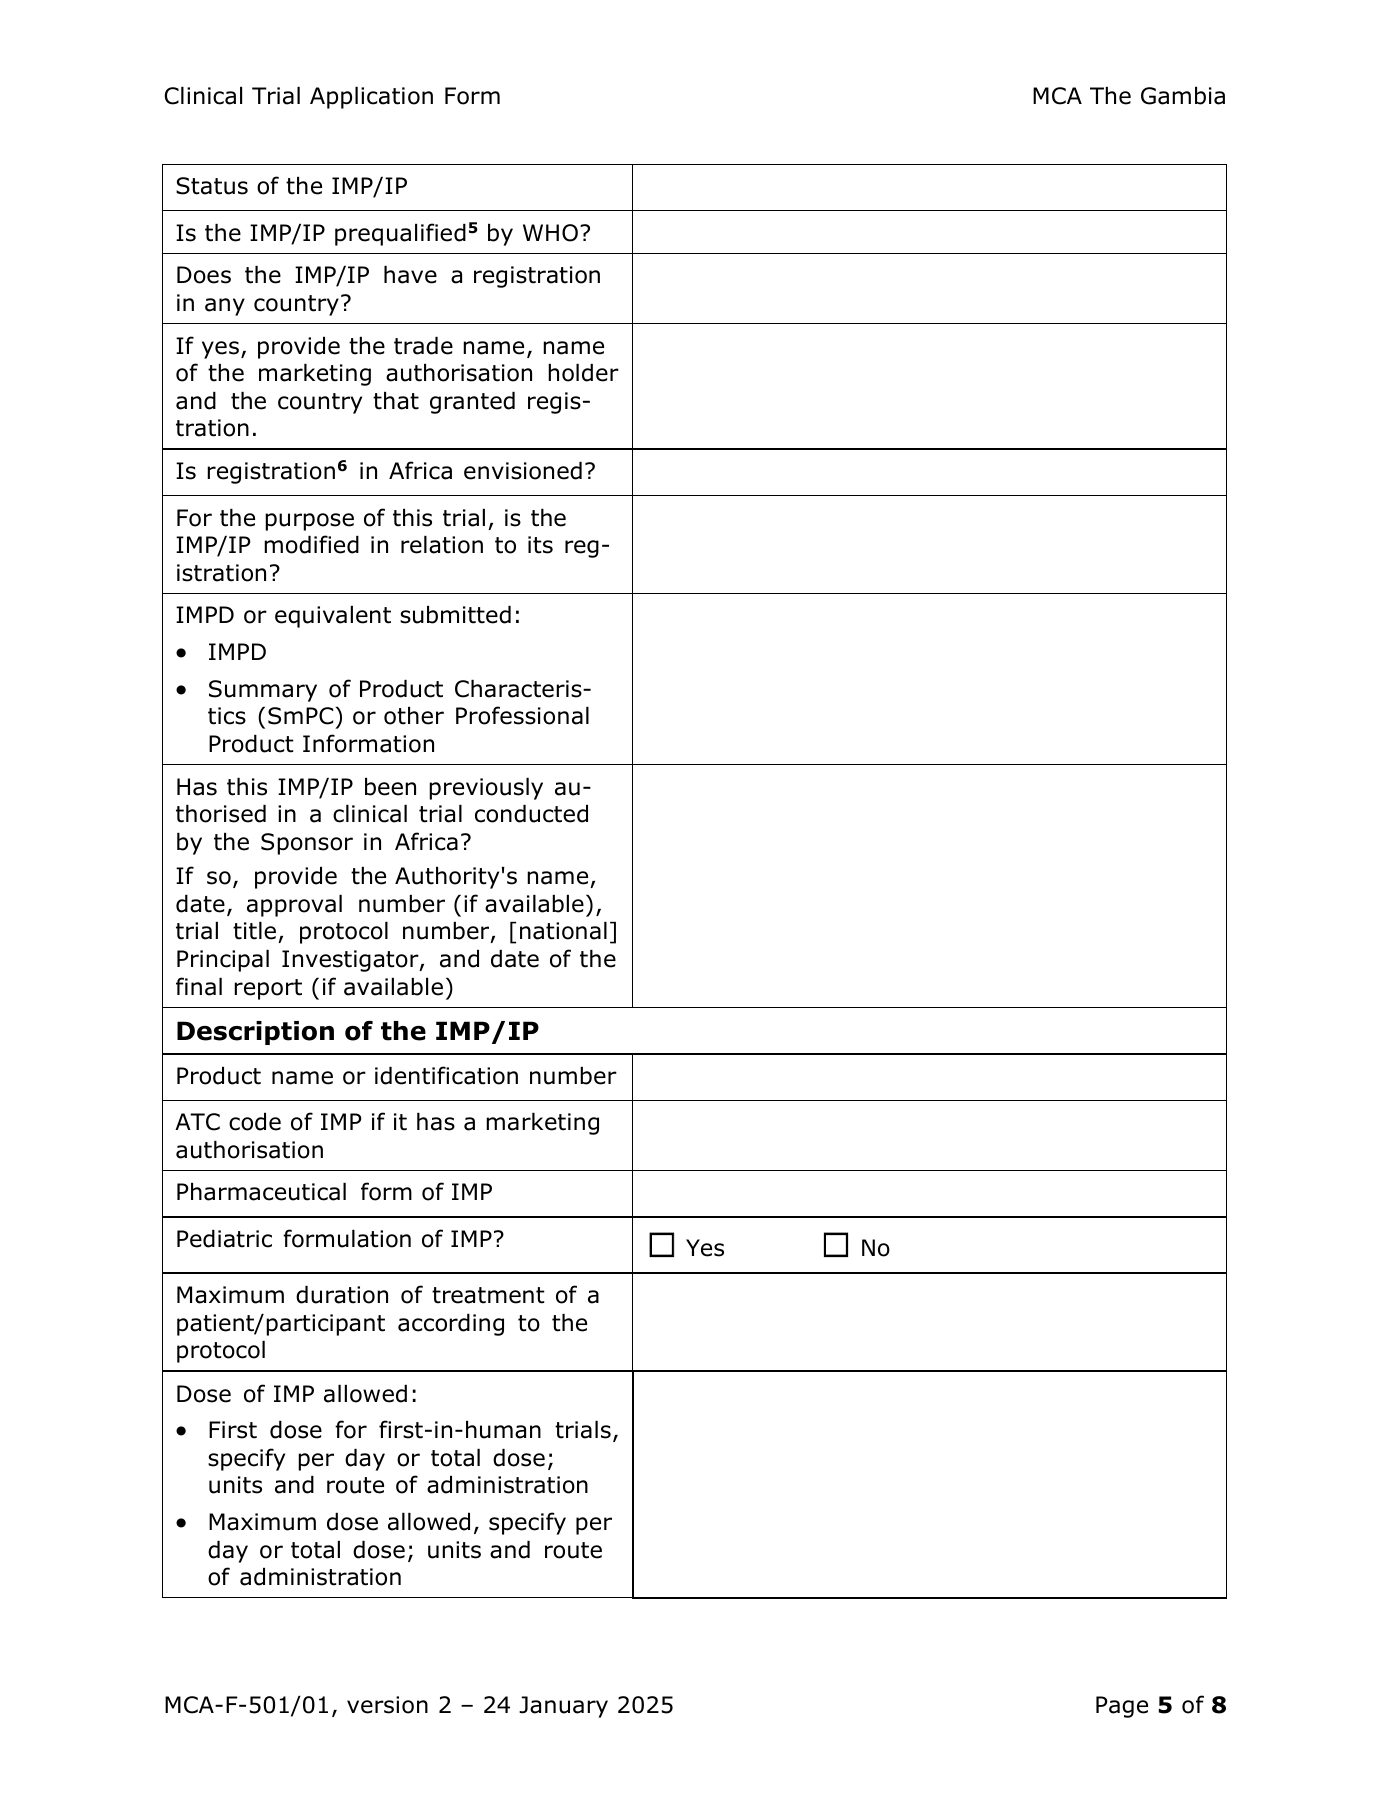
Status of the IMP/IP
Is the IMP/IP prequalified5 by WHO?
Does the IMP/IP have a registration
in any country?
If yes, provide the trade name, name
of the marketing authorisation holder
and the country that granted regis-
tration.
Is registration6 in Africa envisioned?
For the purpose of this trial, is the
IMP/IP modified in relation to its reg-
istration?
IMPD or equivalent submitted:
• IMPD
• Summary of Product Characteris-
tics (SmPC) or other Professional
Product Information
Has this IMP/IP been previously au-
thorised in a clinical trial conducted
by the Sponsor in Africa?
If so, provide the Authority's name,
date, approval number (if available),
trial title, protocol number, [national]
Principal Investigator, and date of the
final report (if available)
Description of the IMP/IP
Product name or identification number
ATC code of IMP if it has a marketing
authorisation
Pharmaceutical form of IMP
Pediatric formulation of IMP? ☐ Yes ☐ No
Maximum duration of treatment of a
patient/participant according to the
protocol
Dose of IMP allowed:
• First dose for first-in-human trials,
specify per day or total dose;
units and route of administration
• Maximum dose allowed, specify per
day or total dose; units and route
of administration
MCA-F-501/01, version 2 – 24 January 2025 Page 5 of 8
Original PDF page 5 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
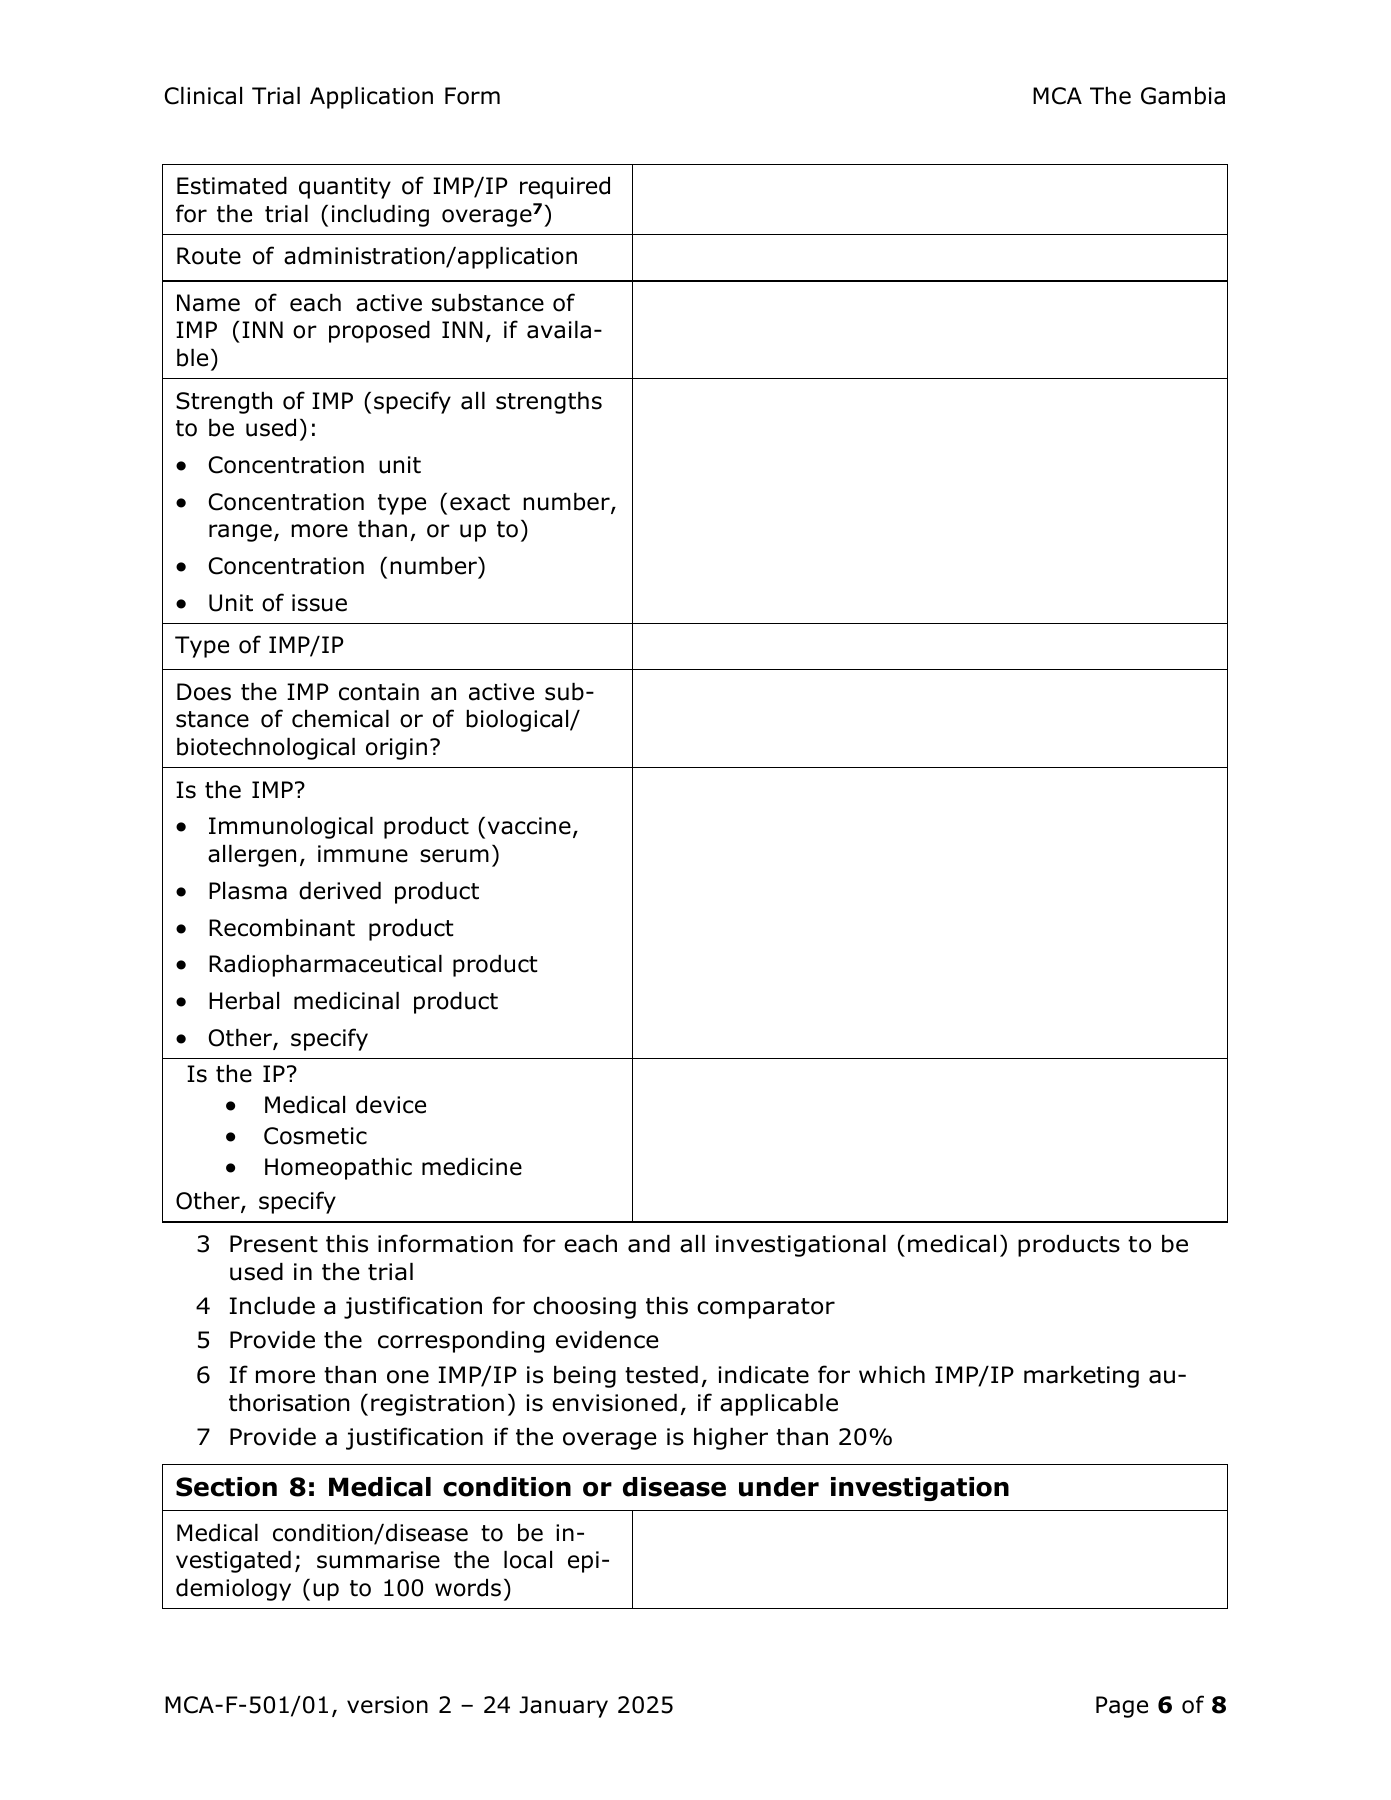
Estimated quantity of IMP/IP required
for the trial (including overage7)
Route of administration/application
Name of each active substance of
IMP (INN or proposed INN, if availa-
ble)
Strength of IMP (specify all strengths
to be used):
• Concentration unit
• Concentration type (exact number,
range, more than, or up to)
• Concentration (number)
• Unit of issue
Type of IMP/IP
Does the IMP contain an active sub-
stance of chemical or of biological/
biotechnological origin?
Is the IMP?
• Immunological product (vaccine,
allergen, immune serum)
• Plasma derived product
• Recombinant product
• Radiopharmaceutical product
• Herbal medicinal product
• Other, specify
Is the IP?
• Medical device
• Cosmetic
• Homeopathic medicine
Other, specify
3 Present this information for each and all investigational (medical) products to be
used in the trial
4 Include a justification for choosing this comparator
5 Provide the corresponding evidence
6 If more than one IMP/IP is being tested, indicate for which IMP/IP marketing au-
thorisation (registration) is envisioned, if applicable
7 Provide a justification if the overage is higher than 20%
Section 8: Medical condition or disease under investigation
Medical condition/disease to be in-
vestigated; summarise the local epi-
demiology (up to 100 words)
MCA-F-501/01, version 2 – 24 January 2025 Page 6 of 8
Original PDF page 6 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
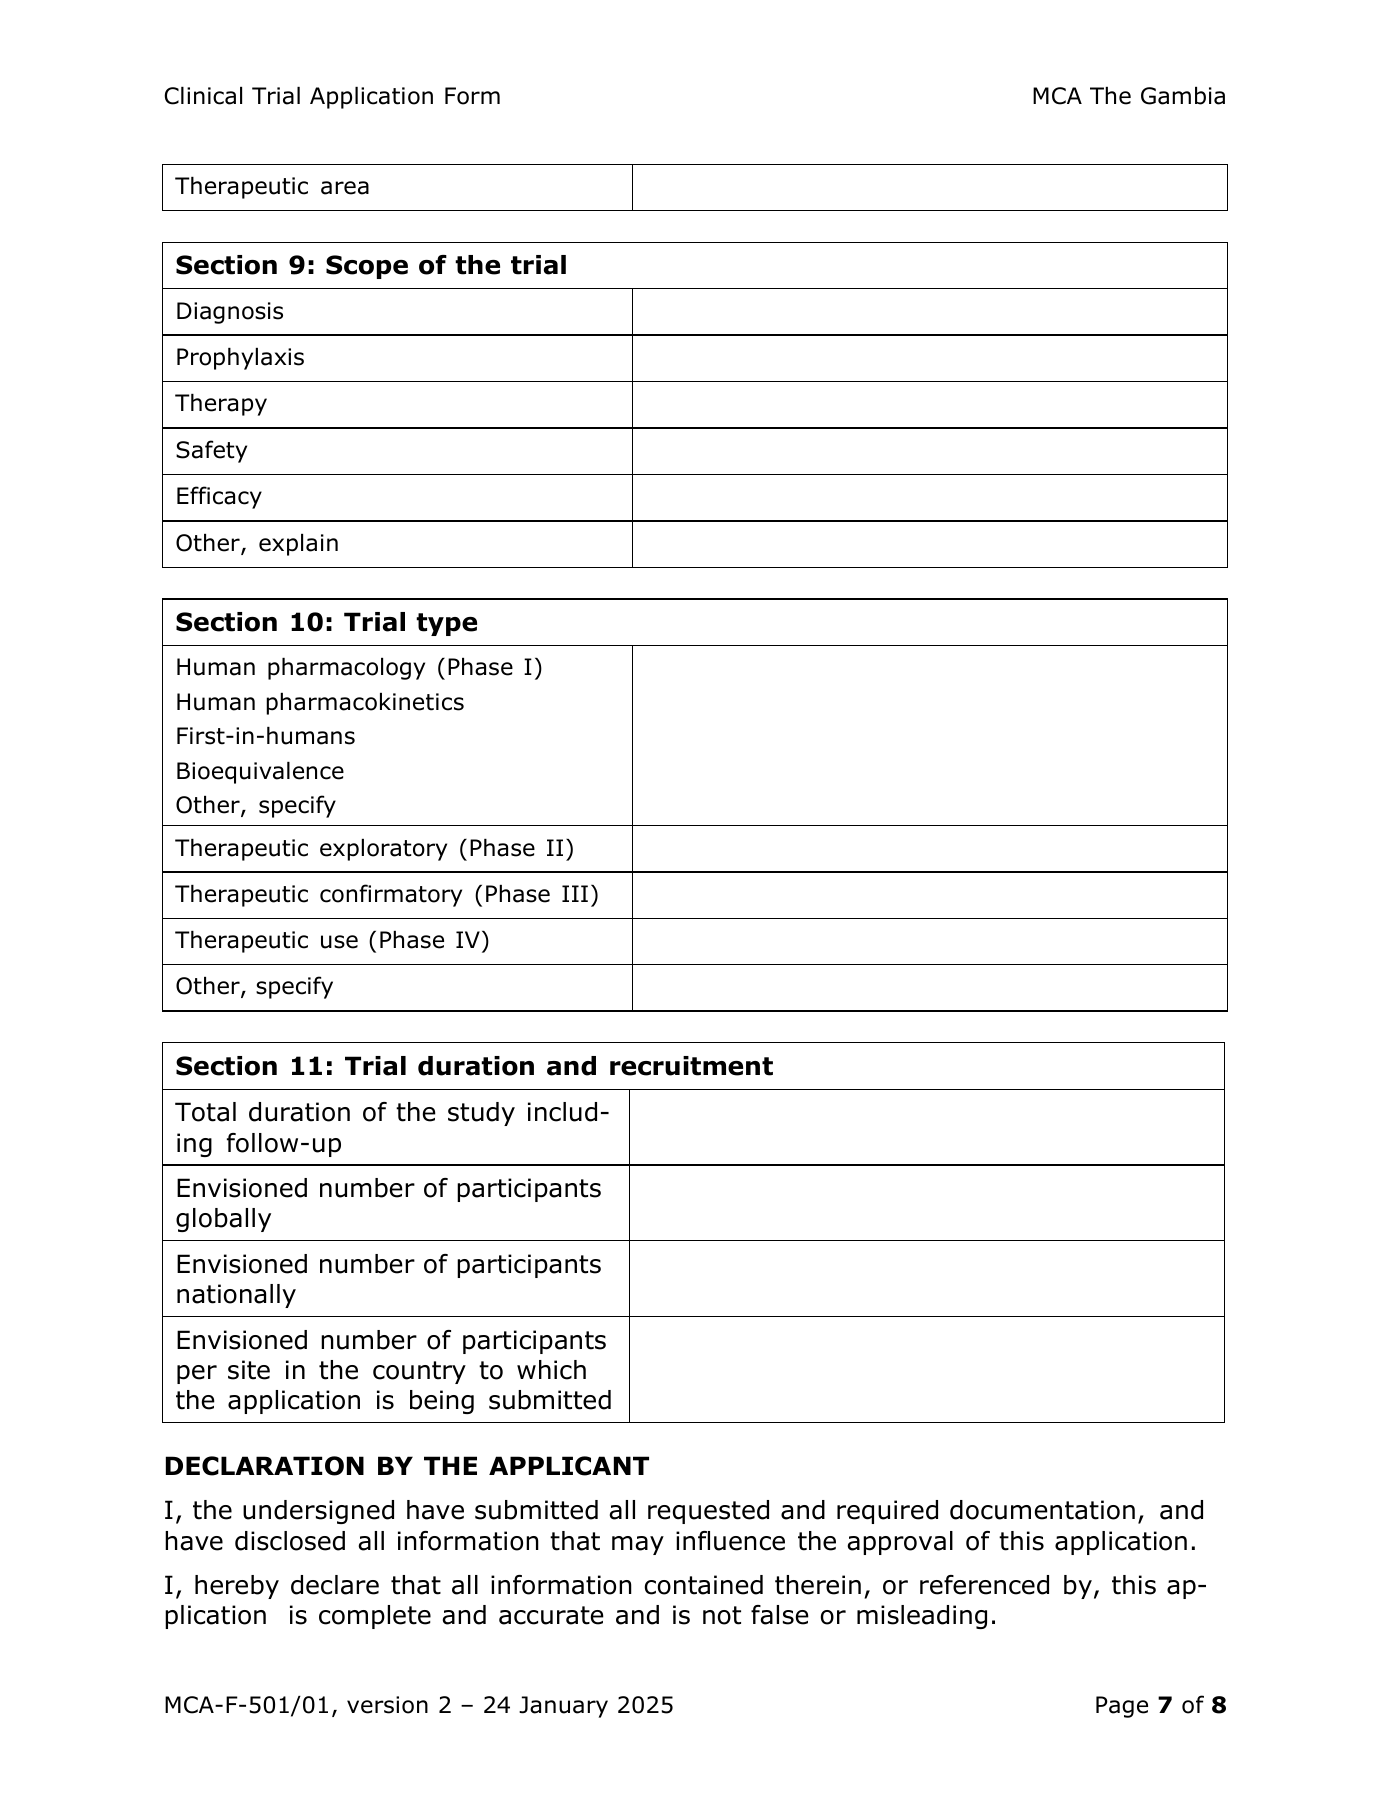
Therapeutic area
Section 9: Scope of the trial
Diagnosis
Prophylaxis
Therapy
Safety
Efficacy
Other, explain
Section 10: Trial type
Human pharmacology (Phase I)
Human pharmacokinetics
First-in-humans
Bioequivalence
Other, specify
Therapeutic exploratory (Phase II)
Therapeutic confirmatory (Phase III)
Therapeutic use (Phase IV)
Other, specify
Section 11: Trial duration and recruitment
Total duration of the study includ-
ing follow-up
Envisioned number of participants
globally
Envisioned number of participants
nationally
Envisioned number of participants
per site in the country to which
the application is being submitted
DECLARATION BY THE APPLICANT
I, the undersigned have submitted all requested and required documentation, and
have disclosed all information that may influence the approval of this application.
I, hereby declare that all information contained therein, or referenced by, this ap-
plication is complete and accurate and is not false or misleading.
MCA-F-501/01, version 2 – 24 January 2025 Page 7 of 8
Original PDF page 7 — retained source fields, tables and layout.
Clinical Trial Application Form MCA The Gambia
I, the undersigned will ensure that if the above-said clinical trial is approved, it will
be conducted according to the protocol submitted, and all applicable legal, good
clinical practice, ethical and regulatory requirements.
Signature of Applicant
Name Signature Date
OFFICIAL USE
Date received: MCA CT Number:
Comments
MCA-F-501/01, version 2 – 24 January 2025 Page 8 of 8
Original PDF page 8 — retained source fields, tables and layout.