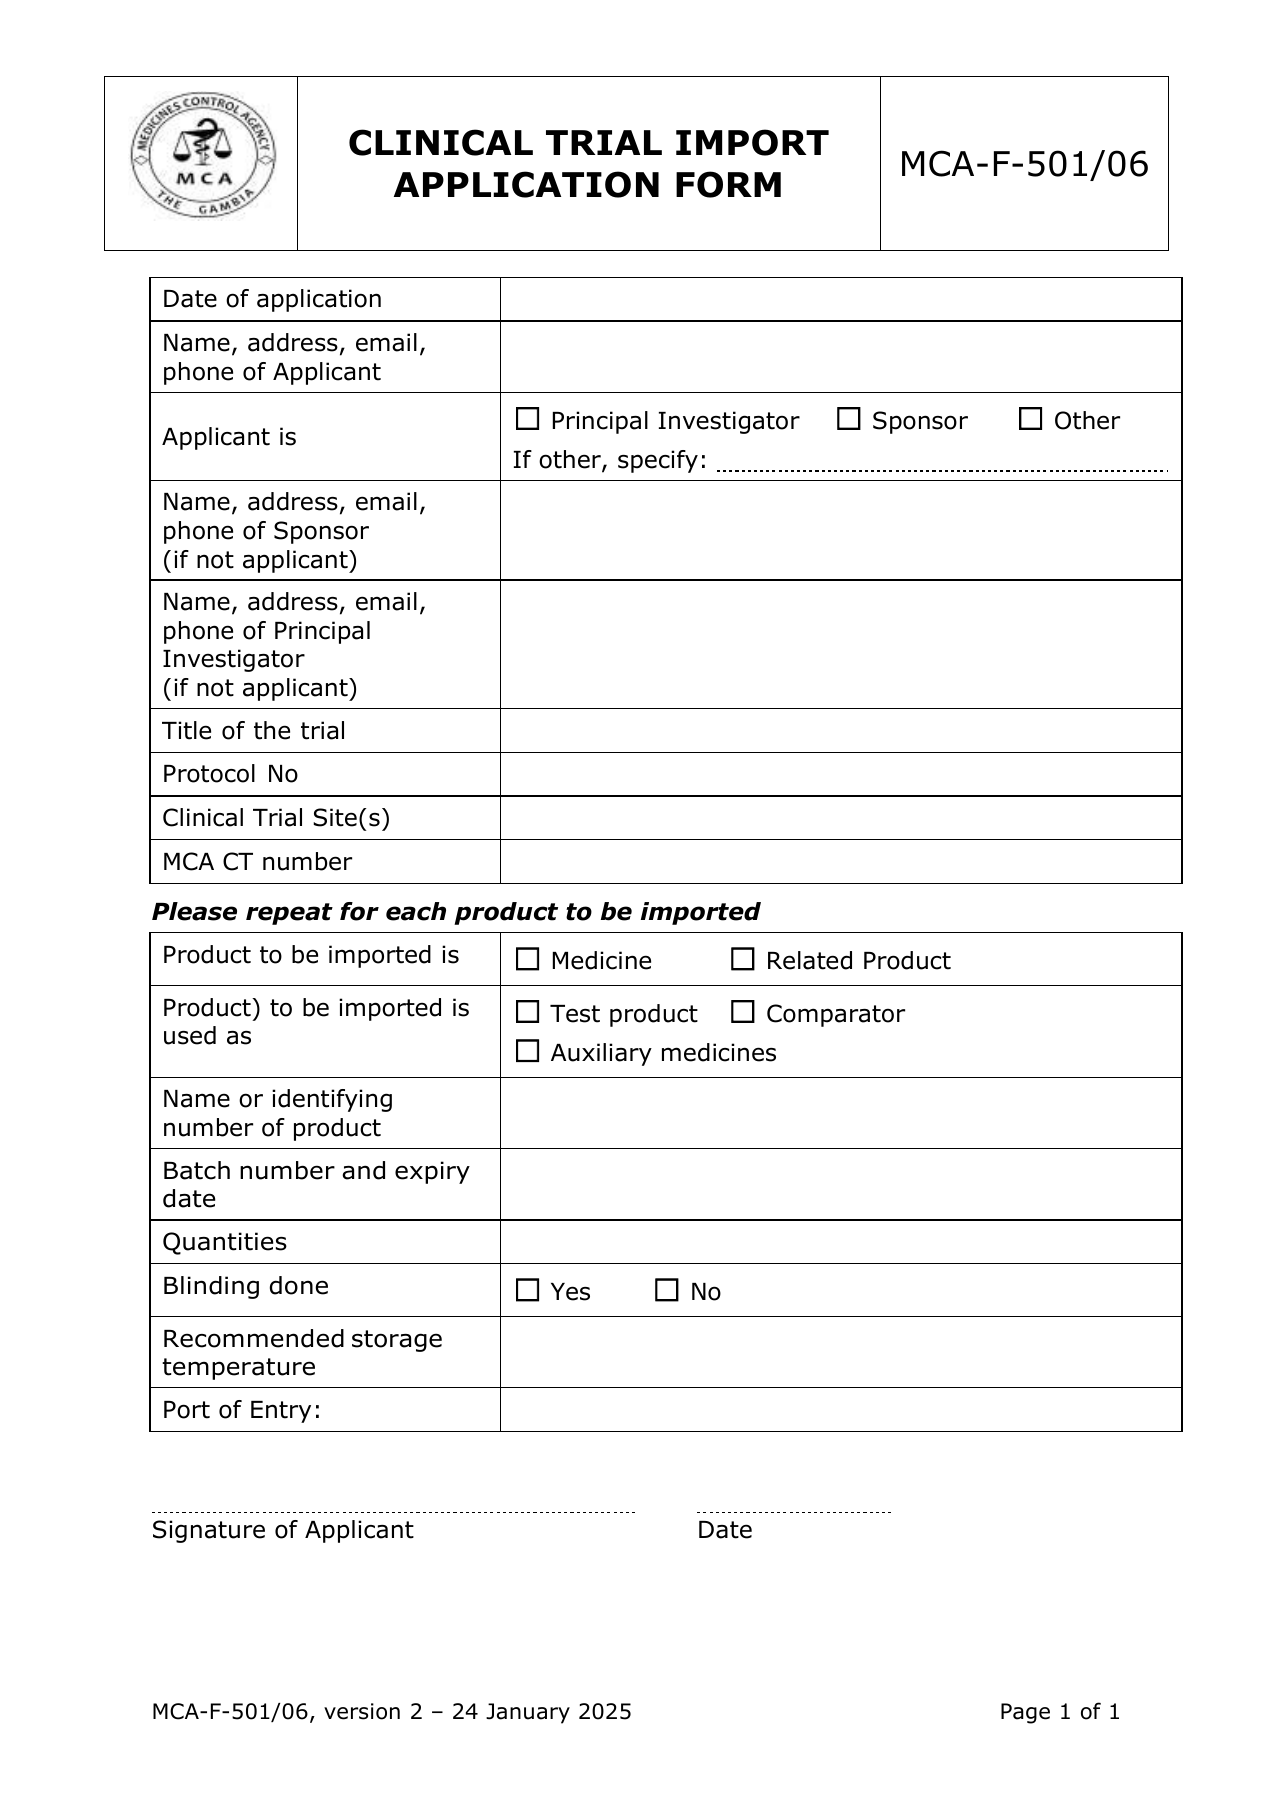
MEDICINES CONTROL AGENCY MCA THE GAMBIA CLINICAL TRIAL IMPORT MCA-F-501/06 APPLICATION FORM Date of application Name, address, email, phone of Applicant ☐ Principal Investigator ☐ Sponsor ☐ Other Applicant is If other, specify: Name, address, email, phone of Sponsor (if not applicant) Name, address, email, phone of Principal Investigator (if not applicant) Title of the trial Protocol No Clinical Trial Site(s) MCA CT number Please repeat for each product to be imported Product to be imported is ☐ Medicine ☐ Related Product Product) to be imported is ☐ Test product ☐ Comparator used as ☐ Auxiliary medicines Name or identifying number of product Batch number and expiry date Quantities Blinding done ☐ Yes ☐ No Recommended storage temperature Port of Entry: Signature of Applicant Date MCA-F-501/06, version 2 – 24 January 2025 Page 1 of 1