MCA-F-501/12, version 2 – 24 January 2025 — Observational Phase IV Clinical Study Application Form
Currentness under review. Whether this instrument remains applicable is under review. Consult the later instruments and source context below before relying on it.
Link directly to a passage with its anchor — for example #pdf-page-1 — to open it highlighted. This reference version is generated from the authority’s publication and does not replace it. Language: English.
Contents
MEDICINES CONTROL AGENCY
MCA
THE GAMBIA
OBSERVATIONAL PHASE IV CLINICAL
MCA-F-501/12
STUDY APPLICATION FORM
MEDICINES CONTROL AGENCY
Off Bertil Harding Highway, Kotu East, Kanifing Municipality, P.O. Box 3162, Serekunda, The Gambia
Website: www.mca.gm; E-mail: info@mca.gm; Tel. No.: +2204380632
*Write NA if an item is not applicable
Section 1: Study identification
Study title
Observation Plan, date, and version1
Study identification, where applicable
Purpose of the study ☐ PASS ☐ PAES ☐ Other
If other, specify:
Status ☐ Commercial ☐ Non-commercial
1
Any translation of the observation plan should be assigned the same date and
version as those in the original document
Section 2: Identification of the Responsible Persons
Name of the responsible person
Qualification
MDCG Registration number, if
applicable
Address
Telephone number
E-mail
Website (if applicable)
Persons the responsible person has delegated functions to2
Name of the organisation
Address
Name of the person
Function
Telephone number
E-mail
2
Repeat as necessary
MCA-F-501/12, version 2 – 24 January 2025 Page 1 of 3
Original PDF page 1 — retained source fields, tables and layout.
Observational Phase IV Clinical Study Application Form MCA The Gambia
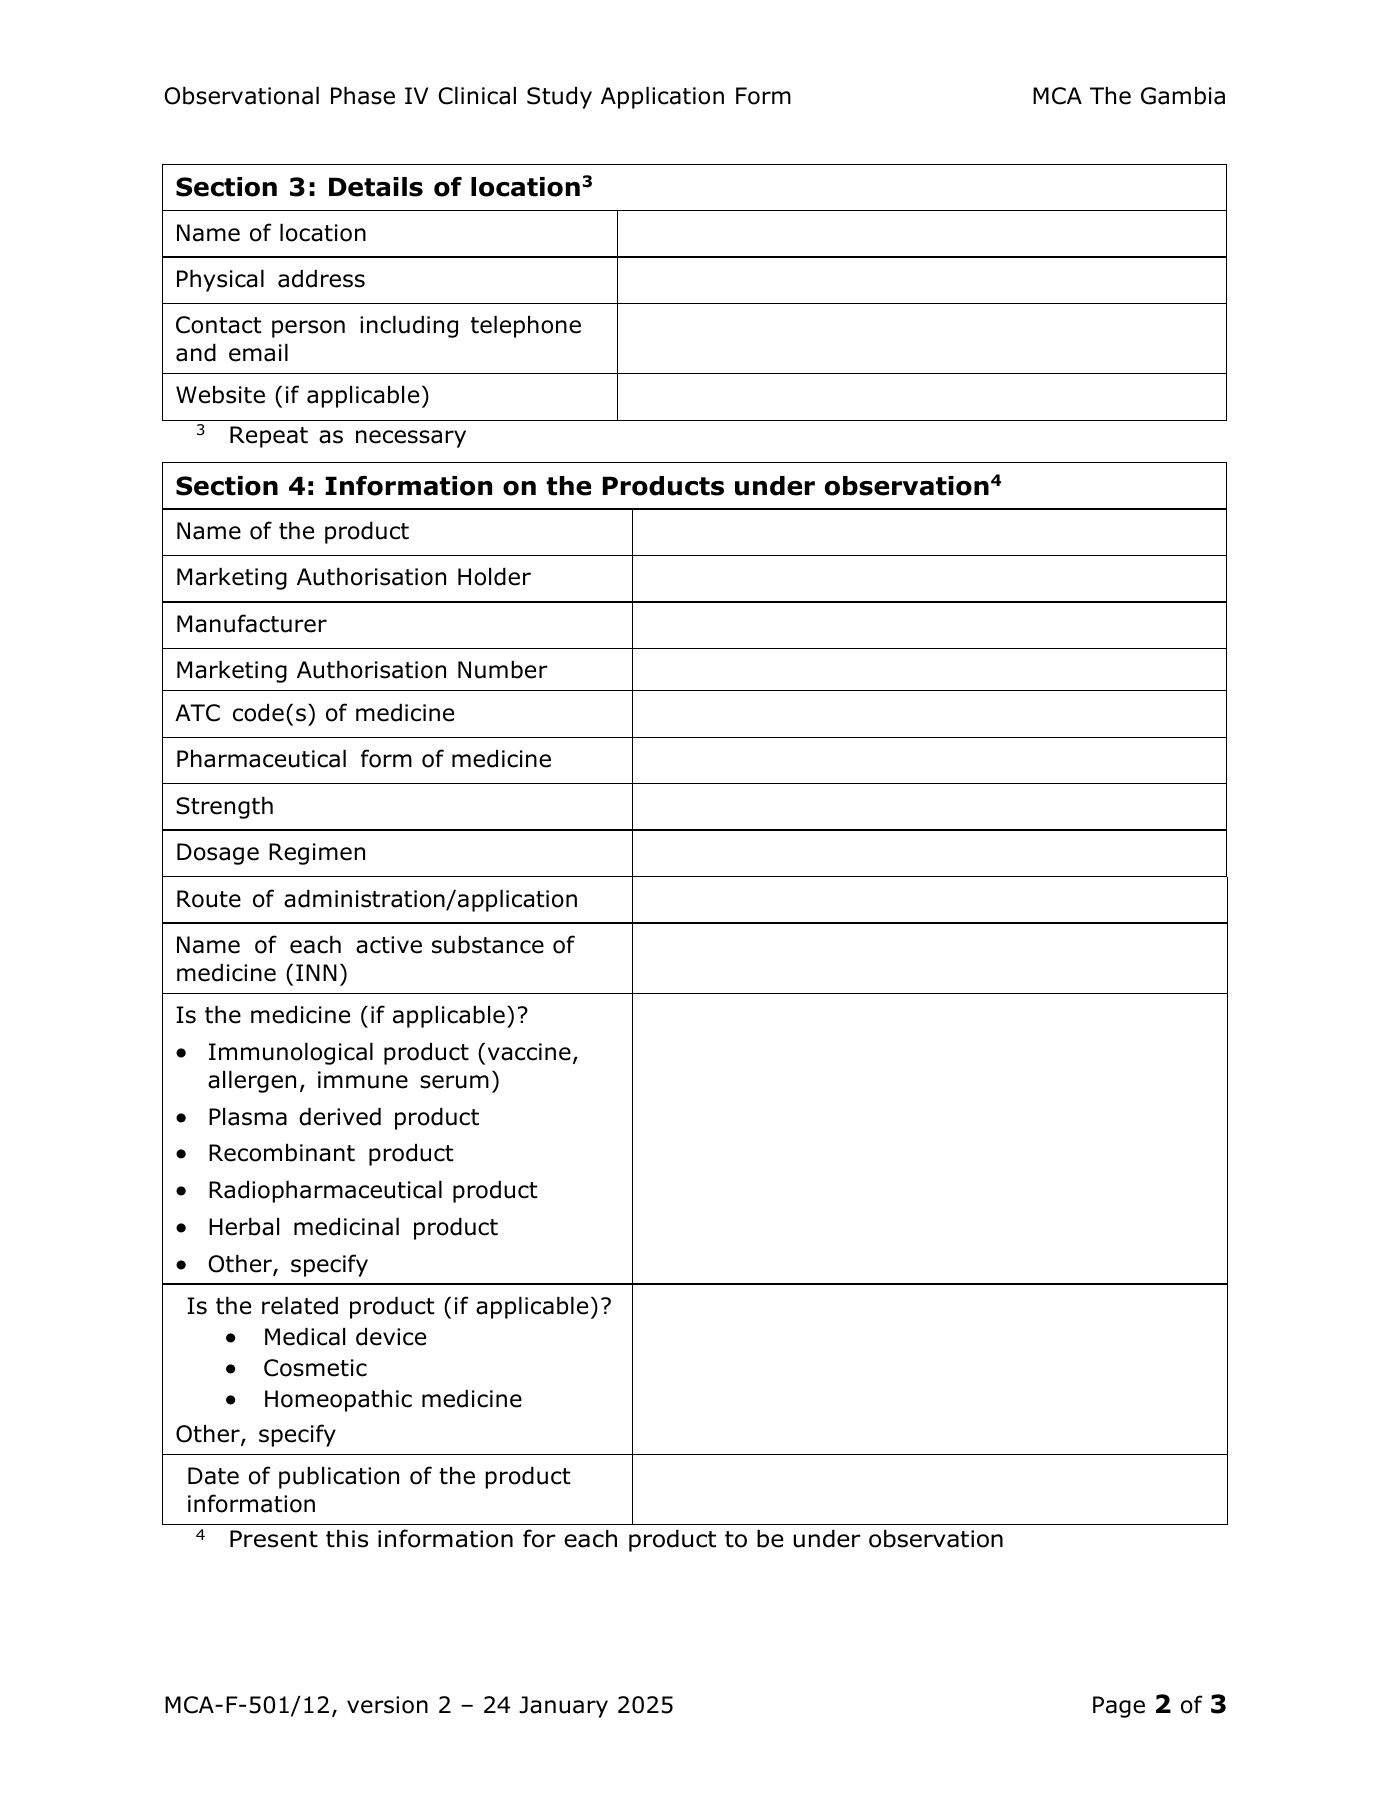
Section 3: Details of location3
Name of location
Physical address
Contact person including telephone
and email
Website (if applicable)
3
Repeat as necessary
Section 4: Information on the Products under observation4
Name of the product
Marketing Authorisation Holder
Manufacturer
Marketing Authorisation Number
ATC code(s) of medicine
Pharmaceutical form of medicine
Strength
Dosage Regimen
Route of administration/application
Name of each active substance of
medicine (INN)
Is the medicine (if applicable)?
• Immunological product (vaccine,
allergen, immune serum)
• Plasma derived product
• Recombinant product
• Radiopharmaceutical product
• Herbal medicinal product
• Other, specify
Is the related product (if applicable)?
• Medical device
• Cosmetic
• Homeopathic medicine
Other, specify
Date of publication of the product
information
4
Present this information for each product to be under observation
MCA-F-501/12, version 2 – 24 January 2025 Page 2 of 3
Original PDF page 2 — retained source fields, tables and layout.
Observational Phase IV Clinical Study Application Form MCA The Gambia
Section 5: Information on the patients5
Medical condition or disease5 the
product is prescribed for
Number of patients
5
Present this information for each product to be under observation
Section 6: Study duration
Total duration of the study
Start date
End date
DECLARATION BY THE APPLICANT
I, the undersigned have submitted all requested and required documentation, and
have disclosed all information that may influence the approval of this application.
I, hereby declare that all information contained therein, or referenced by, this
application is complete and accurate and is not false or misleading.
Signature of the Responsible Person
Name Signature Date
OFFICIAL USE
Date received: MCA-number:
Comments
MCA-F-501/12, version 2 – 24 January 2025 Page 3 of 3
Original PDF page 3 — retained source fields, tables and layout.