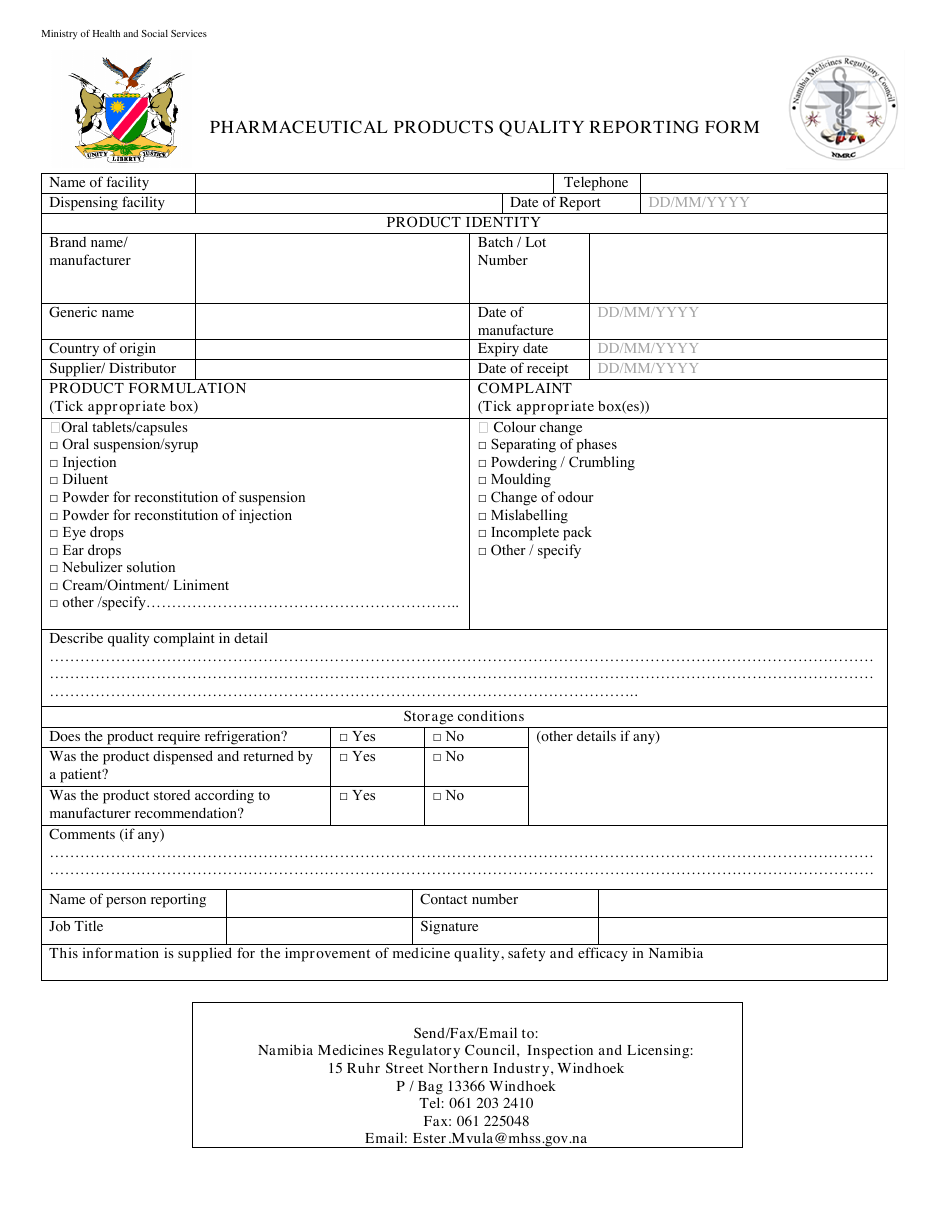
Ministry of Health and Social Services PHARMACEUTICAL PRODUCTS QUALITY REPORTING FORM Name of facility Telephone Dispensing facility Date of Report DD/MM/YYYY PRODUCT IDENTITY Brand name/ Batch / Lot manufacturer Number Generic name Date of DD/MM/YYYY manufacture Country of origin Expiry date DD/MM/YYYY Supplier/ Distributor Date of receipt DD/MM/YYYY PRODUCT FORMULATION COMPLAINT (Tick appropriate box) (Tick appropriate box(es)) □ Oral tablets/capsules □ Colour change □ Oral suspension/syrup □ Separating of phases □ Injection □ Powdering / Crumbling □ Diluent □ Moulding □ Powder for reconstitution of suspension □ Change of odour □ Powder for reconstitution of injection □ Mislabelling □ Eye drops □ Incomplete pack □ Ear drops □ Other / specify □ Nebulizer solution □ Cream/Ointment/ Liniment □ other /specify…………………………………………………….. Describe quality complaint in detail ……………………………………………………………………………………………………………………………………………… ……………………………………………………………………………………………………………………………………………… …………………………………………………………………………………………………….. Storage conditions Does the product require refrigeration? □ Yes □ No (other details if any) Was the product dispensed and returned by □ Yes □ No a patient? Was the product stored according to □ Yes □ No manufacturer recommendation? Comments (if any) ……………………………………………………………………………………………………………………………………………… ……………………………………………………………………………………………………………………………………………… Name of person reporting Contact number Job Title Signature This information is supplied for the improvement of medicine quality, safety and efficacy in Namibia Send/Fax/Email to: Namibia Medicines Regulatory Council, Inspection and Licensing: 15 Ruhr Street Northern Industry, Windhoek P / Bag 13366 Windhoek Tel: 061 203 2410 Fax: 061 225048 Email: Ester.Mvula@mhss.gov.na