Government Notice 9 of 2022 — Pharmacy and Medicines Regulatory Authority (Fees and Forms) Regulations, 2022
Currentness under review. Whether this instrument remains applicable is under review. Consult the later instruments and source context below before relying on it.
Link directly to a passage with its anchor — for example #pdf-page-1 — to open it highlighted. This reference version is generated from the authority’s publication and does not replace it. Language: English.
Contents
17
The Malawi Gazette Supplement, dated 8th April, 2022, containing
Regulations, Rules, etc. (No. 6A)
GOVERNMENT NOTICE NO. 9
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS, 2022
IN EXERCISE of powers conferred by section 129 of the Pharmacy and Medicines
Regulatory Authority Act, I, KHUMBIZE KANDODO CHIPONDA, Minister of Health, make the
following Regulations—
Citation
1. These Regulations may be cited as the Pharmacy and Medicines
Regulatory Authority (Fees and Forms) Regulations, 2022.
Fees
2. The Authority shall charge the fees specified in the First Schedule,
in respect of the matters correspondingly specified herein.
Surcharge
3.—(1) The Authority shall charge a surcharge to any person who fails to
pay retention fees as specified in the First Schedule.
(2) A person who fails to pay retention fees—
(a) within three months of the commencement of the Authority’s
financial year, shall pay a surcharge of fifty percent of the retention fees
payable; and
(b) after three months of the commencement of the Authority’s
financial year, shall pay a surcharge of one hundred percent of the
retention fees payable.
Forms
4. The forms set out in the Second Schedule shall be used for the
purposes of the Act.
FIRST SCHEDULE
reg. 2
PRESCRIBED FEES
Matter | Fees
1. Registration fees for pharmacy personnel: on application for registration including
issuance of a certificate—
(a) pharmacist—
(i) Malawian pharmacist, including internship | K50,000 00
(ii) non-Malawian pharmacist including vetting | US$1,000 00
(iii) Malawian pharmacist re-examination fees, per subject | K25,000 00
(iv) non-Malawian pharmacist re-examination fees, per subject | US$215 00
(v) non-Malawian volunteer pharmacist | US$250 00
Government Notice 9 of 2022 — official PDF page 1; original table columns, symbols and diagram connections
18 8th April, 2022
Matter | Fees
(b) pharmacy technologist—
(i) Malawian technologist | K30,000 00
(ii) non-Malawian technologist, including vetting | US$700 00
(iii) Malawian technologist re-examination fees, per subject | K10, 000 00
(iv) non-Malawian technologist re-examination fees, per subject | US$175 00
(c) pharmacy assistant—
(i) Malawian pharmacy assistant | K20,000 00
(ii) non-Malawian pharmacy assistant, including vetting | US$400 00
(iii) Malawian pharmacy assistant re-examination fees, per subject | K8,000 00
(iv) non-Malawian pharmacy assistant re-examination fees, per subject | US$100 00
(d) medical representative—
(i) Malawian medical representative | K150,000 00
(ii) non-Malawian medical representative | US$700 00
2. Retention fees for pharmacy personnel—
(a) pharmacist—
(i) Malawian pharmacist | K30,000 00
(ii) non-Malawian pharmacist | US$550 00
(iii) non-Malawian volunteer pharmacist | US$250 00
(b) pharmacy technologist—
(i) Malawian technologist | K20,000 00
(ii) non-Malawian technologist | US$300 00
(c) pharmacy assistant—
(i) Malawian pharmacy assistant | K15,000 00
(ii) non-Malawian pharmacy assistant | US$300 00
(d) medical representatives—
(i) Malawian medical representative | K75,000 00
(ii) non-Malawian medical representative | US$300 00
3. Licencing of premises—
(a) manufacturing licence—
(i) inspection and processing for oral dosage forms (solids and liquids) | K1,500,000 00
(ii) inspection and processing for external preparations | K1,300,000 00
(iii) inspection and processing for sterile preparations | K1,700,000 00
(iv) inspection and processing for primary and secondary packaging | K1,000,000 00
(v) re-inspection of premises, if previously failed | *cost of travel
Government Notice 9 of 2022 — official PDF page 2; original table columns, symbols and diagram connections
8th April, 2022 19
Matter | Fees
(b) wholesale pharmacy licence—
(i) inspection and processing | K760,000 00
(ii) re-inspection fees of premises, if previously failed | *cost of travel
(c) retail pharmacy licence—
(i) inspection and processing | K385,000 00
(ii) re-inspection fees of premises, if previously failed | *cost of travel
(d) medicine store licence or veterinary shop licence—
(i) inspection and processing | K200,000 00
(ii) re-inspection fees of premises if previously failed | *cost of travel
(e) dispensing licence—
(i) inspection and processing of licence for a facility with an admission service | K335,000 00
(ii) inspection and processing of licence for a facility without an admission service | K200,000.00
(iii) re-inspection fees of premises, if previously failed | *cost of travel
(f) medical device: wholesale, retail and cosmetic shop—
(i) inspection and processing | K710,000 00
(ii) re-inspection fees of premises, if previously failed | *cost of travel
*Cost of travel shall be determined by agreement between the Authority and the applicant.
4. Retention fees for premises—
(a) manufacturing licence—
(i) premises with oral dosage forms (solids and liquids) | K350,000 00
(ii) premises with external preparations | K260,000 00
(iii) premises with sterile preparations | K400,000 00
(iv) primary packaging only | K200,000 00
(v) secondary packaging only | K120,000 00
(b) wholesale pharmacy licence—
(i) retention fees | K320,000 00
(ii) inspection and relocation processing | K520,000 00
(c) retail pharmacy licence—
(i) retention fees | K160,000 00
(ii) inspection and relocation processing | K235,000 00
(d) medicine store and veterinary shop licence—
(i) retention fees | K60,000 00
(ii) inspection and relocation processing | K160,000 00
(e) medical device: wholesale, retail and cosmetic shop—
(i) retention fees | K320,000 00
(ii) inspection and relocation processing | K560,000 00
Government Notice 9 of 2022 — official PDF page 3; original table columns, symbols and diagram connections
20 8th April, 2022
Matter | Fees
(f) dispensing licence—
(i) retention for a facility with an admission service | K160,000 00
(ii) inspection and relocation processing | K235,000 00
(iii) retention for a facility without and admission service | K55,000 00
(iv) inspection and relocation processing | K155,000 00
5. Registration of medicinal products—
(a) human, veterinary and herbal medicinal products—
(i) human or veterinary product manufactured in Malawi | K300,000 00
(ii) human or veterinary product manufactured in Malawi (expedited processing of application) | K600,000 00
(iii) human or veterinary product manufactured outside Malawi | US$1500 00
(iv) human or veterinary product manufactured outside Malawi (expedited processing of application) | US$3000 00
(v) herbal product manufactured in Malawi | K80,000 00
(vi) herbal product manufactured outside Malawi | US$1,100 00
(vii) human or veterinary product packed in Malawi but manufactured outside Malawi | US$450 00
6. *Retention fees for medicinal products—
(a) human or veterinary and herbal medicinal products—
(i) human or veterinary product manufactured in Malawi | K150,000 00
(ii) human or veterinary product manufactured outside Malawi | US$700 00
(iii) herbal product manufactured in Malawi | K50,000 00
(iv) herbal product manufactured outside Malawi | US$450 00
*Products not retained for one year without submission of withdrawal notice, shall attract
payment of the retention fees in arrears first, before re-instatement on the Register.
7. Registration of allied substances—
(a) medical devices, condoms, surgical sundries—
(i) class I | US$500 00
(ii) class II | US$750 00
(iii) class III | US$1500 00
(b) traditional medicines and nutritional supplements—
(i) nutritional and traditional medicinal product manufactured in Malawi | K80,000 00
(ii) nutritional and traditional medicinal product manufactured outside Malawi | US$500 00
(c) cosmetic products—
(i) cosmetic products manufactured in Malawi | K80,000 00
(ii) cosmetic products manufactured outside Malawi | US$500 00
Government Notice 9 of 2022 — official PDF page 4; original table columns, symbols and diagram connections
8th April, 2022 21
Matter | Fees
(d) disinfectants and reagents—
(i) disinfectants and reagents manufactured in Malawi | K80,000 00
(ii) disinfectants and reagents manufactured outside Malawi | US$400 00
(e) feed additives and supplements—
(i) feed additives and supplements manufactured in Malawi | K100,000 00
(ii) feed additives and supplements manufactured outside Malawi | US$500 00
8. Retention fees for allied substances—
(a) medical devices, condoms and surgical sundries—
(i) class I | US$200 00
(ii) class II | US$ 300 00
(iii) class III | US$700 00
(b) traditional medicines and nutritional supplements—
(i) nutritional and traditional medicinal product manufactured in Malawi | K50,000 00
(ii) nutritional and traditional medicinal product manufactured outside Malawi | US$200 00
(c) cosmetic products—
(i) cosmetic products manufactured in Malawi | K50,000 00
(ii) cosmetic products manufactured outside Malawi | US$500 00
(d) disinfectants and reagents—
(i) disinfectants and reagents manufactured in Malawi | K50,000 00
(ii) disinfectants and reagents manufactured outside Malawi | US$150 00
(e) feed additives and supplements—
(i) feed additives and supplements manufactured in Malawi | K80,000 00
(ii) feed additives and supplements manufactured outside Malawi | US$250 00
9. Analysis of samples by the quality control laboratory—
(a) routine drug analysis per batch—
(i) sample originating from a Malawian | *K5,700 – K615,000
(ii) sample originating from a non-Malawian | *US$36 00 – US$300 00
(b) male latex condoms per batch—
(i) sample originating from a Malawian | K560,000 00
(ii) sample originating from a non-Malawian | US$700 00
(c) samples analysis at laboratories outside the Authority | cost of analysis plus 12% service charge
Government Notice 9 of 2022 — official PDF page 5; original table columns, symbols and diagram connections
22 8th April, 2022
Matter | Fees
(d) re-analysis of samples at owner’s or importer’s request—
(i) sample originating from a Malawian | K700,000 00
(ii) sample originating from a non-Malawian | US$880 00
(e) detailed certificate of analysis at the owner of sample’s request—
(i) sample originating from a Malawian | K300,000 00
(ii) sample originating from a non-Malawian | US$380 00
(f) analysis of sample under investigation—
(i) sample originating from a Malawian | K160,000 00
(ii) sample originating from a non-Malawian | US$200 00
*The fees for routine drug analysis shall depend on the type of test and dosage form as
shall be indicated on a tabulated chart published by the Authority from time to time.
10. Applications, registration, renewal and amendment of clinical trials—
(a) application, review and registration of a clinical trial | 5% of total budget
(b) annual renewal of a clinical trial | US$2,200 00
(c) amendments to a clinical trial | US$300 00
(d) veterinary clinical trial | 5% of total budget
(e) annual renewal of veterinary clinical trial | US$750 00
11. Assessment and issuance of permit for importation, exportation
and waivers on importation for medicines and allied substances—
(a) import or export permit for registered medicines (per batch) | 1.5% of total invoice value
(b) verification fees for commercial consignments and donations
to commercial organizations | 1.0% of total invoice value
(c) importation of unregistered medicines or allied substances
from authorized sources | 6.0% of total invoice value
(d) verification and approval fees for a consignment of
medicines and/ or allied substances for disasters, outbreak
and raw materials | exempted
(e) verification fees for donations to non-profit making organizations | K30,000 00
(f) narcotic drugs or psychotropic substances permit | K30,000 00
12. Vetting of health products promotional materials, per language—
(a) written materials—
(i) originating within Malawian | K40,000 00
(ii) originating outside Malawi | US$100 00
Government Notice 9 of 2022 — official PDF page 6; original table columns, symbols and diagram connections
8th April, 2022 23
Matter | Fees
(b) audio, video and written scripts—
(i) originating within Malawi | K80,000 00
(ii) originating outside Malawi | US$100 00
(c) posters or billboards on any medium including the internet—
(i) originating within Malawi | K80,000 00
(ii) originating outside Malawi | US$100 00
(d) posters on vehicles—
(i) originating within Malawi | K40,000 00
(ii) originating outside Malawi | US$100 00
(e) t-shirts—
(i) originating within Malawi | K20,000 00
(ii) originating outside Malawi | US$100 00
(f) other materials such as caps, wall clocks, watches, umbrellas or bags—
(i) originating within Malawi | K20,000 00
(ii) originating outside Malawi | US$100 00
13. Fees for the Authority’s publications—
(a) set of Statutes and Statutory Instruments | K21,000 00
(b) Code of Ethics | K3,000 00
(c) Dangerous drugs register | K10,000 00
(d) pharmacist register book | K3,000 00
14. Miscellaneous—
(a) inspection on demand | K200,000 00
(b) supervision of medicine destruction | K60,000 00
(c) medicine disposal certificate | K30,000 00
(d) licence re-print | K50,000 00
(e) licence re-issue following revocation | K200,000 00
15. Licencing of pharmacy colleges and curriculum review—
(a) inspection and processing fees for pharmacy colleges | K400,000 00
(b) curriculum review of diploma and certificate courses | K2,000,000 00
(c) curriculum review of degree courses | K3,000,000 00
16. Upon inspection of foreign manufacturing sites to assess current
good manufacturing practice (cGMP) inspection & certificate—
(a) manufacturer within the Southern Africa Development Community | US$ 3500 00
(b) manufacturer from the rest of Africa | US$ 5,000 00
(c) manufacturer from outside Africa | US$6,500 00
Government Notice 9 of 2022 — official PDF page 7; original table columns, symbols and diagram connections
24 8th April, 2022
SECOND SCHEDULE reg. 4
FORMS
Form No. 1
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR REGISTRATION AS A PHARMACIST, PHARMACY
TECHNOLOGIST, PHARMACY ASSISTANT OR MEDICAL REPRESENTATIVE*
(Sections 25 and 39)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
(*Delete whichever is not applicable)
1. Name and address of applicant (in block letters)—
(a) Surname...........................................................................................
(b) First names ......................................................................................
(c) Postal address....................................................................................
(d) Telephone number...............................................................................
2. Date of birth ......................................................................................
3. Sex (male/female) .................................................................................
4. Nationality ........................................................................................
5. Application for registration in the register of ................................................
6. Academic qualifications (certificates, diplomas, degrees) and institutions attended
(school, university, college)—
Qualification | Year | Institution and Country
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
Government Notice 9 of 2022 — official PDF page 8; original table columns, symbols and diagram connections
8th April, 2022 25
7. Professional qualifications (with dates and institutions attended)—
Qualification | Year | Institution/Body
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
........................ | ........... | ........................
8. Present employer and address—
........................................................................................................
........................................................................................................
9. I, the above-mentioned applicant, hereby apply for registration on the aforementioned
register and submit herewith—
*(a) the prescribed application fee of K............................................................
*(b) the prescribed registration fee of K....................................................., and
*(c) the following documents in support of my application:.....................................
........................................................................................................
10. Declaration—
I, the above-mentioned applicant, hereby solemnly and sincerely declare that the
information I have given above is true in every respect to the best of my knowledge and
belief and that I have read the Act and the Regulations made under the Act and
understand that, if registered, I shall be bound thereby and by any amendments thereto,
for as long as my name shall remain on the aforementioned register.
Declared at ........................................ by..................................................
Signature of applicant
before me ........................................ at .....................................................
on this ........ day of ........................................, 20 ......
........................................
Commissioner for Oaths
11. FOR OFFICE USE ONLY—
(a) Date of approval of application ................................................................
(b) Registration number ................................ Certificate number..........................
(c) Receipt Numbers of application and registration fees.........................................
(d) Remarks
........................................................................................................
Government Notice 9 of 2022 — official PDF page 9; original table columns, symbols and diagram connections
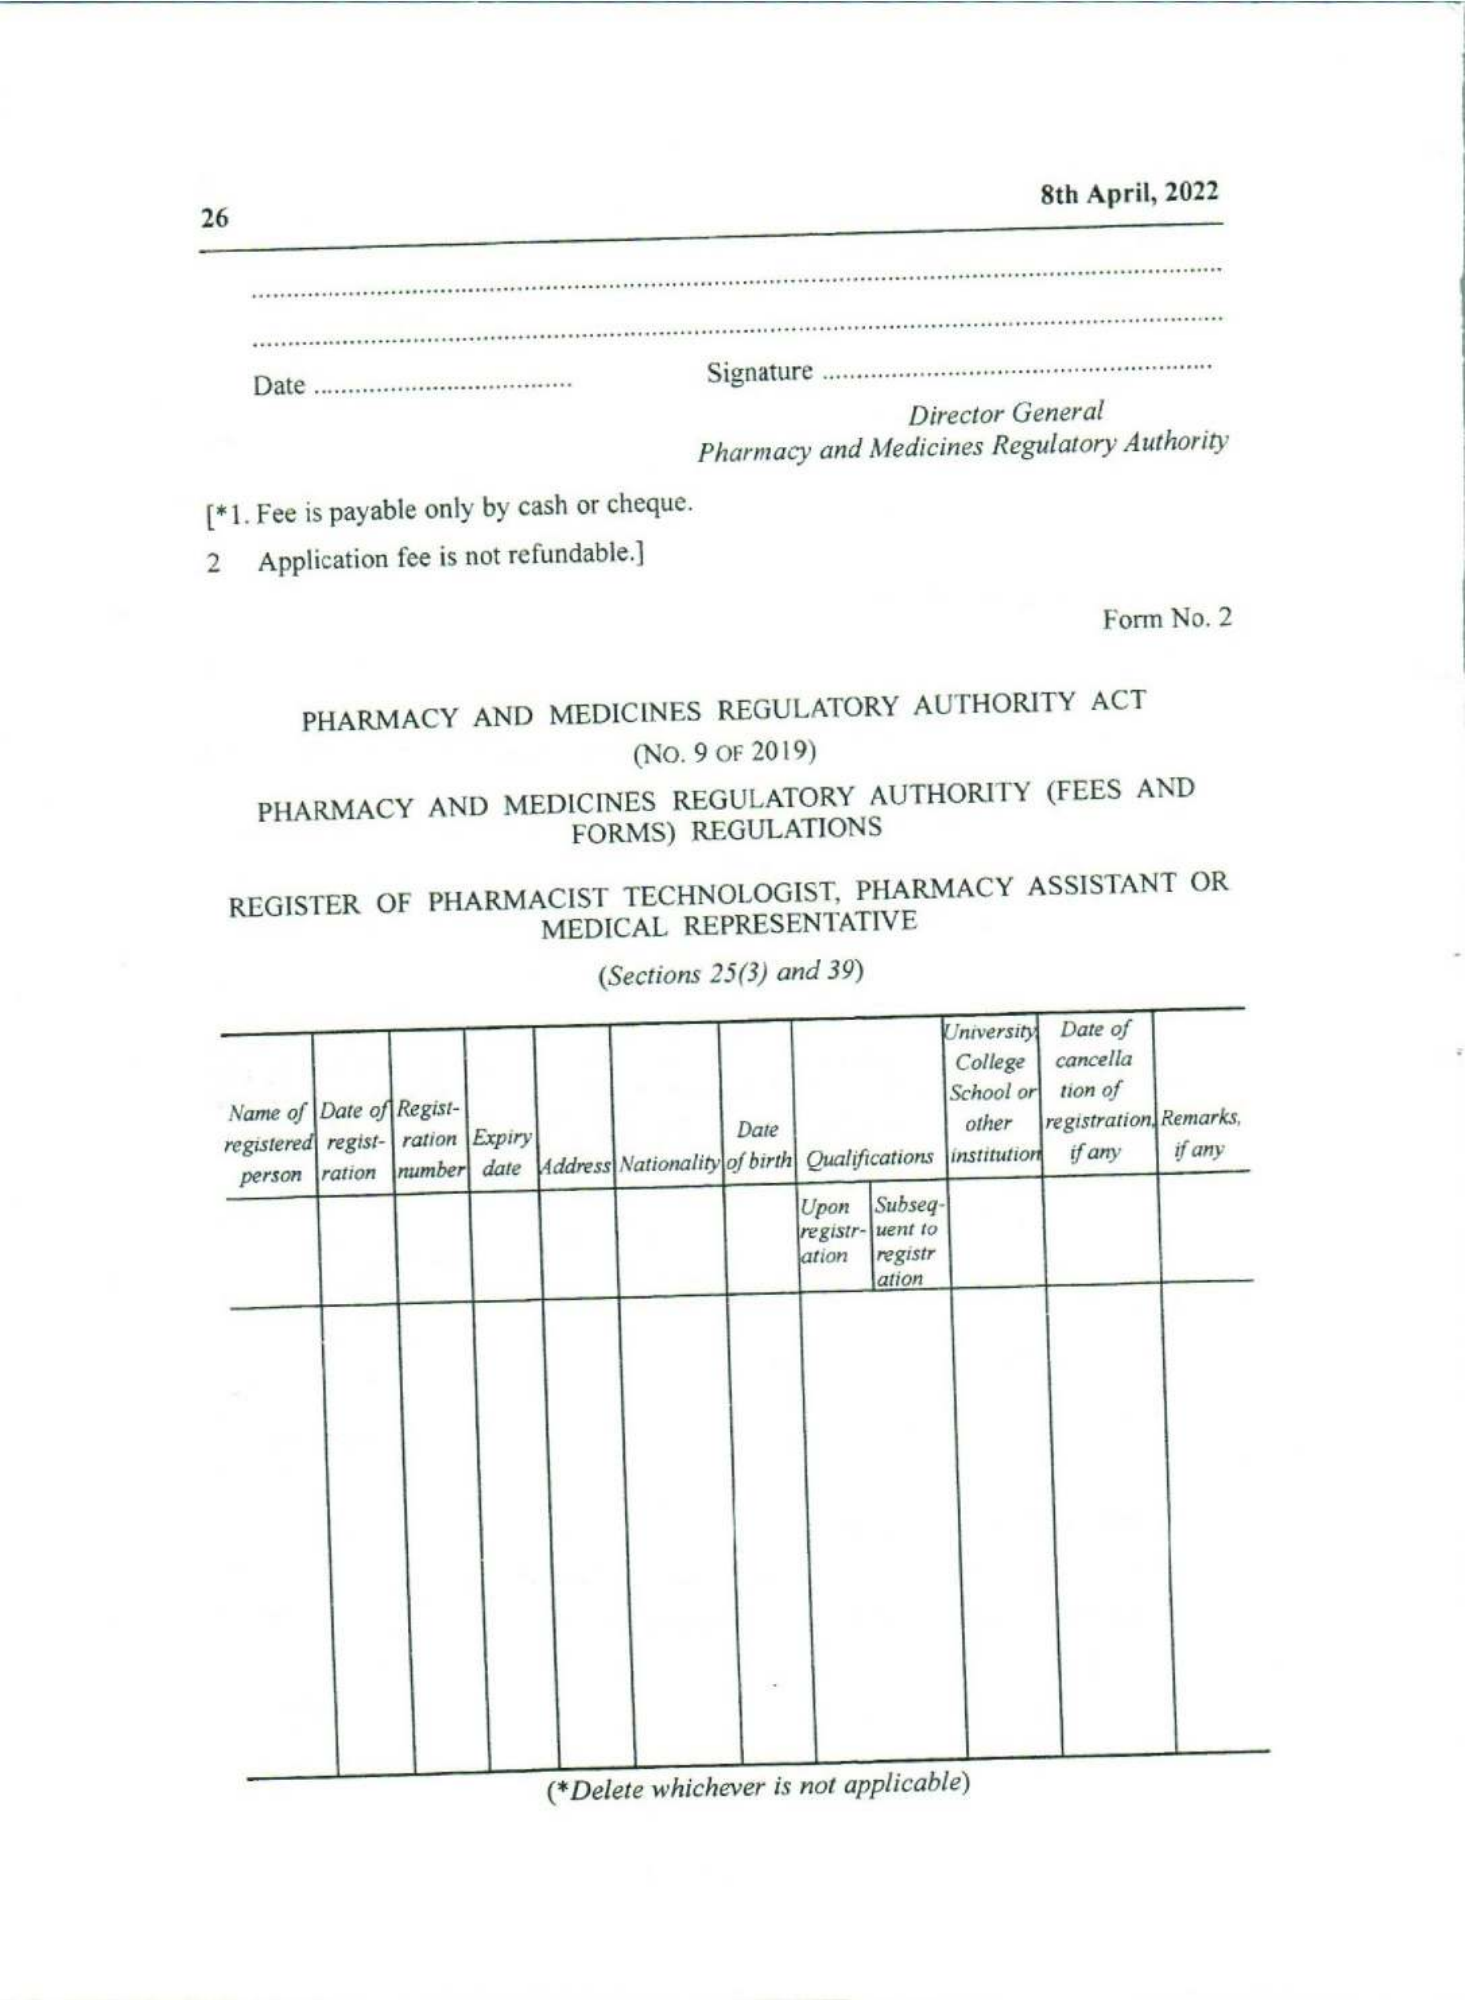
26 8th April, 2022
........................................................................................................
........................................................................................................
Date ........................................ Signature ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 2
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
REGISTER OF PHARMACIST TECHNOLOGIST, PHARMACY ASSISTANT OR
MEDICAL REPRESENTATIVE
(Sections 25(3) and 39)
Name of registered person | Date of registration | Registration number | Expiry date | Address | Nationality | Date of birth | Qualifications | | University College School or other institutions | Date of cancellation of registration if any | Remarks, if any
| | | | | | | Upon registration | Subsequent to registration | | |
(*Delete whichever is not applicable)
Government Notice 9 of 2022 — official PDF page 10; original table columns, symbols and diagram connections
8th April, 2022 27
Form No. 3
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
CERTIFICATE OF REGISTRATION OF A PHARMACIST, PHARMACY
TECHNOLOGIST, PHARMACY ASSISTANT OR MEDICAL REPRESENTATIVE*
(Sections 26 and 39)
Registration number ............................ Certificate number ................................
This is to certify that ..................................................................................
is this ........ day of ....................................,20............. registered on the register of
........................................................................................................
kept and maintained by the Pharmacy and Medicines Regulatory Authority in accordance
with the provisions of the Pharmacy and Medicines Regulatory Authority Act and the
Regulations made thereunder.
Valid until ........................................, 20 ..........
Dated .........................................................
.................................... ....................................
Director General Chairperson
Common Seal
(*Delete whichever is not applicable)
Form No. 4
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR RETENTION OF NAME OF REGISTERED PHARMACIST,
REGISTERED PHARMACY TECHNOLOGIST, REGISTERED PHARMACY
ASSISTANT OR REGISTERED MEDICAL REPRESENTATIVE*
(Sections 27 and 39)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
Government Notice 9 of 2022 — official PDF page 11; original table columns, symbols and diagram connections
28 8th April, 2022
(*Delete whichever is not applicable)
1. Surname ...........................................................................................
2. First names ........................................................................................
3. Postal address .....................................................................................
4. Date of Birth ......................................................................................
5. Sex (male/female) .................................................................................
6. Nationality .........................................................................................
7. Registration number ................................ dated ............................,20..........
8. Certificate number................................ dated ............................, 20 ..........
9. Application for retention of name on the ........................................................
In respect of ...........................................................................................
........................................................................................................
(name of registered Pharmacist, registered Pharmacy Technologist, registered Pharmacy
Assistant or registered medical representative)
10. I, the above-mentioned applicant, hereby apply for retention of my name on the
aforementioned register and submit therefor—
*(a) application fee of K ...................................................................... and
*(b) retention fee of K...............................................................................
Dated this .................... day of ........................................, 20 ..........
........................................
Signature of applicant
11. FOR OFFICE USE ONLY—
(a) Date of approval of application ................................................................
(b) Registration number ......................Certificate number ............................
(c) Receipt numbers of application and retention fees ............................................
(d) Remarks ..........................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Government Notice 9 of 2022 — official PDF page 12; original table columns, symbols and diagram connections
8th April, 2022 29
Form No. 5
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE A RETAIL
PHARMACY BUSINESS IS TO BE CARRIED ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of business ..................................................................................
2. Name of applicant ..................................................................................
3. Email address ....................................Telephone number...............................
4. Postal address......................................................................................
5. Location of premises on which a retail pharmacy business it to be carried (Town, Street,
Plot No.) (Include a sketch map)....................................................................
........................................................................................................
........................................................................................................
........................................................................................................
6. Where the applicant is a company—
(a) state registration number of company under the Act........................................
(b) state name and certificate number of registered pharmacist under whose personal
management and control the affairs of the company would be subject to ...........
........................................................................................................
(c) attach a copy of the certificate of incorporation of the company
........................................................................................................
........................................................................................................
7. Name and number of certificate of registration of a registered pharmacist having
control of the premises referred to in paragraph 5 ..................................................
........................................................................................................
8. I, the above-mentioned applicant, submit herewith the licencing application fee of
K ............................
Date ........................................ ........................................
Signature of applicant
Government Notice 9 of 2022 — official PDF page 13; original table columns, symbols and diagram connections
30 8th April, 2022
9. FOR OFFICE USE ONLY—
(a) Date of inspection of premises ................................................................
(b) Remarks ..........................................................................................
(c) Date of approval of application ................................................................
(d) Licence number ..................................................................................
(e) Receipt number of licencing application fees ..................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 6
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE A RETAIL-
PHARMACY BUSINESS IS TO BE CARRIED ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of business ..................................................................................
2. Name of applicant..................................................................................
3. Postal address......................................................................................
4. Email address................................Telephone number...................................
5. Previous location of the retail pharmacy.........................................................
6. Location of premises to which the retail pharmacy is re-located (city/town, street, plot
no.) (include a sketch map)..........................................................................
........................................................................................................
........................................................................................................
7. Where the applicant is a company—
(a) state registration number of company under the Act ........................................
Government Notice 9 of 2022 — official PDF page 14; original table columns, symbols and diagram connections
8th April, 2022 31
(b) state name and certificate number of registered pharmacist under whose personal
management and control the affairs of the company would be subject to
........................................................................................................
(c) attach a copy of the certificate of incorporation of the company
........................................................................................................
8. Name and number of certificate of registration of a registered pharmacist having
control of the premises referred to in paragraph 6..................................................
........................................................................................................
9. I, the above-mentioned applicant, submit herewith an application fee of
K ........................................
Date ........................................ ........................................
Signature of applicant
10. FOR OFFICE USE ONLY—
(a) Application fee of K..............................................................................
(b) Date of inspection of premises ................................................................
(c) Remarks ..........................................................................................
(d) Date of approval of application ................................................................
(e) Licence number ..................................................................................
(f) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 7
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE WHOLESALE
PHARMACY BUSINESS IS TO BE CARRIED ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
Government Notice 9 of 2022 — official PDF page 15; original table columns, symbols and diagram connections
32 8th April, 2022
1. Name of business..................................................................................
2. Name of applicant..................................................................................
3. Postal address......................................................................................
4. Email address........................................ Telephone number ........................
5. Location of premises on which wholesale pharmacy business is to be carried out
(city/town, street, plot no.) include a sketch map)
........................................................................................................
........................................................................................................
6. Where the applicant is a company—
(a) state the registration number of company under the Act;....................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of certificate of incorporation of the company
........................................................................................................
........................................................................................................
7. Name and registration number of supervising pharmacist having control of the
premises referred to in paragraph 5..................................................................
........................................................................................................
........................................................................................................
8. I, the abovementioned applicant, submit herewith a licence application fee of
K ........................................
Date ........................................ ........................................
Signature of applicant
9. FOR OFFICE USE ONLY—
(a) Licence application fee of K ....................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Licence number ..................................................................................
(f) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
Government Notice 9 of 2022 — official PDF page 16; original table columns, symbols and diagram connections
8th April, 2022 33
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 8
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 19 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE WHOLESALE
PHARMACY BUSINESS IS TO BE CARRIED ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of business..................................................................................
2. Name of applicant..................................................................................
3. Postal address......................................................................................
4. Email address........................................ Telephone number ........................
5. Previous location of the wholesale pharmacy.....................................................
........................................................................................................
6. Location of premises on which wholesale pharmacy business is re-located (city/town,
street, plot no.) (include a sketch map)
........................................................................................................
........................................................................................................
7. Where the applicant is a company—
(a) state the registration number of company under the Act:....................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of certificate of incorporation of the company
........................................................................................................
........................................................................................................
Government Notice 9 of 2022 — official PDF page 17; original table columns, symbols and diagram connections
34 8th April, 2022
8. Name and registration number of supervising pharmacist having control of the
premises referred to in paragraph 6..............................................................
........................................................................................................
........................................................................................................
9. I, the abovementioned applicant, submit herewith an application fee of K ...................
Date ........................................ ........................................
Signature of applicant
10. FOR OFFICE USE ONLY—
(a) Application fee of K ...........................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of premises................................................................
(d) Date of approval of application...............................................................
(e) Licence number ..................................................................................
(f) Receipt number of application .................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. The Application fee is not refundable.]
Form No. 9
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF MEDICINE DEVICE WHOLESALER
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
LILONGWE 3
Government Notice 9 of 2022 — official PDF page 18; original table columns, symbols and diagram connections
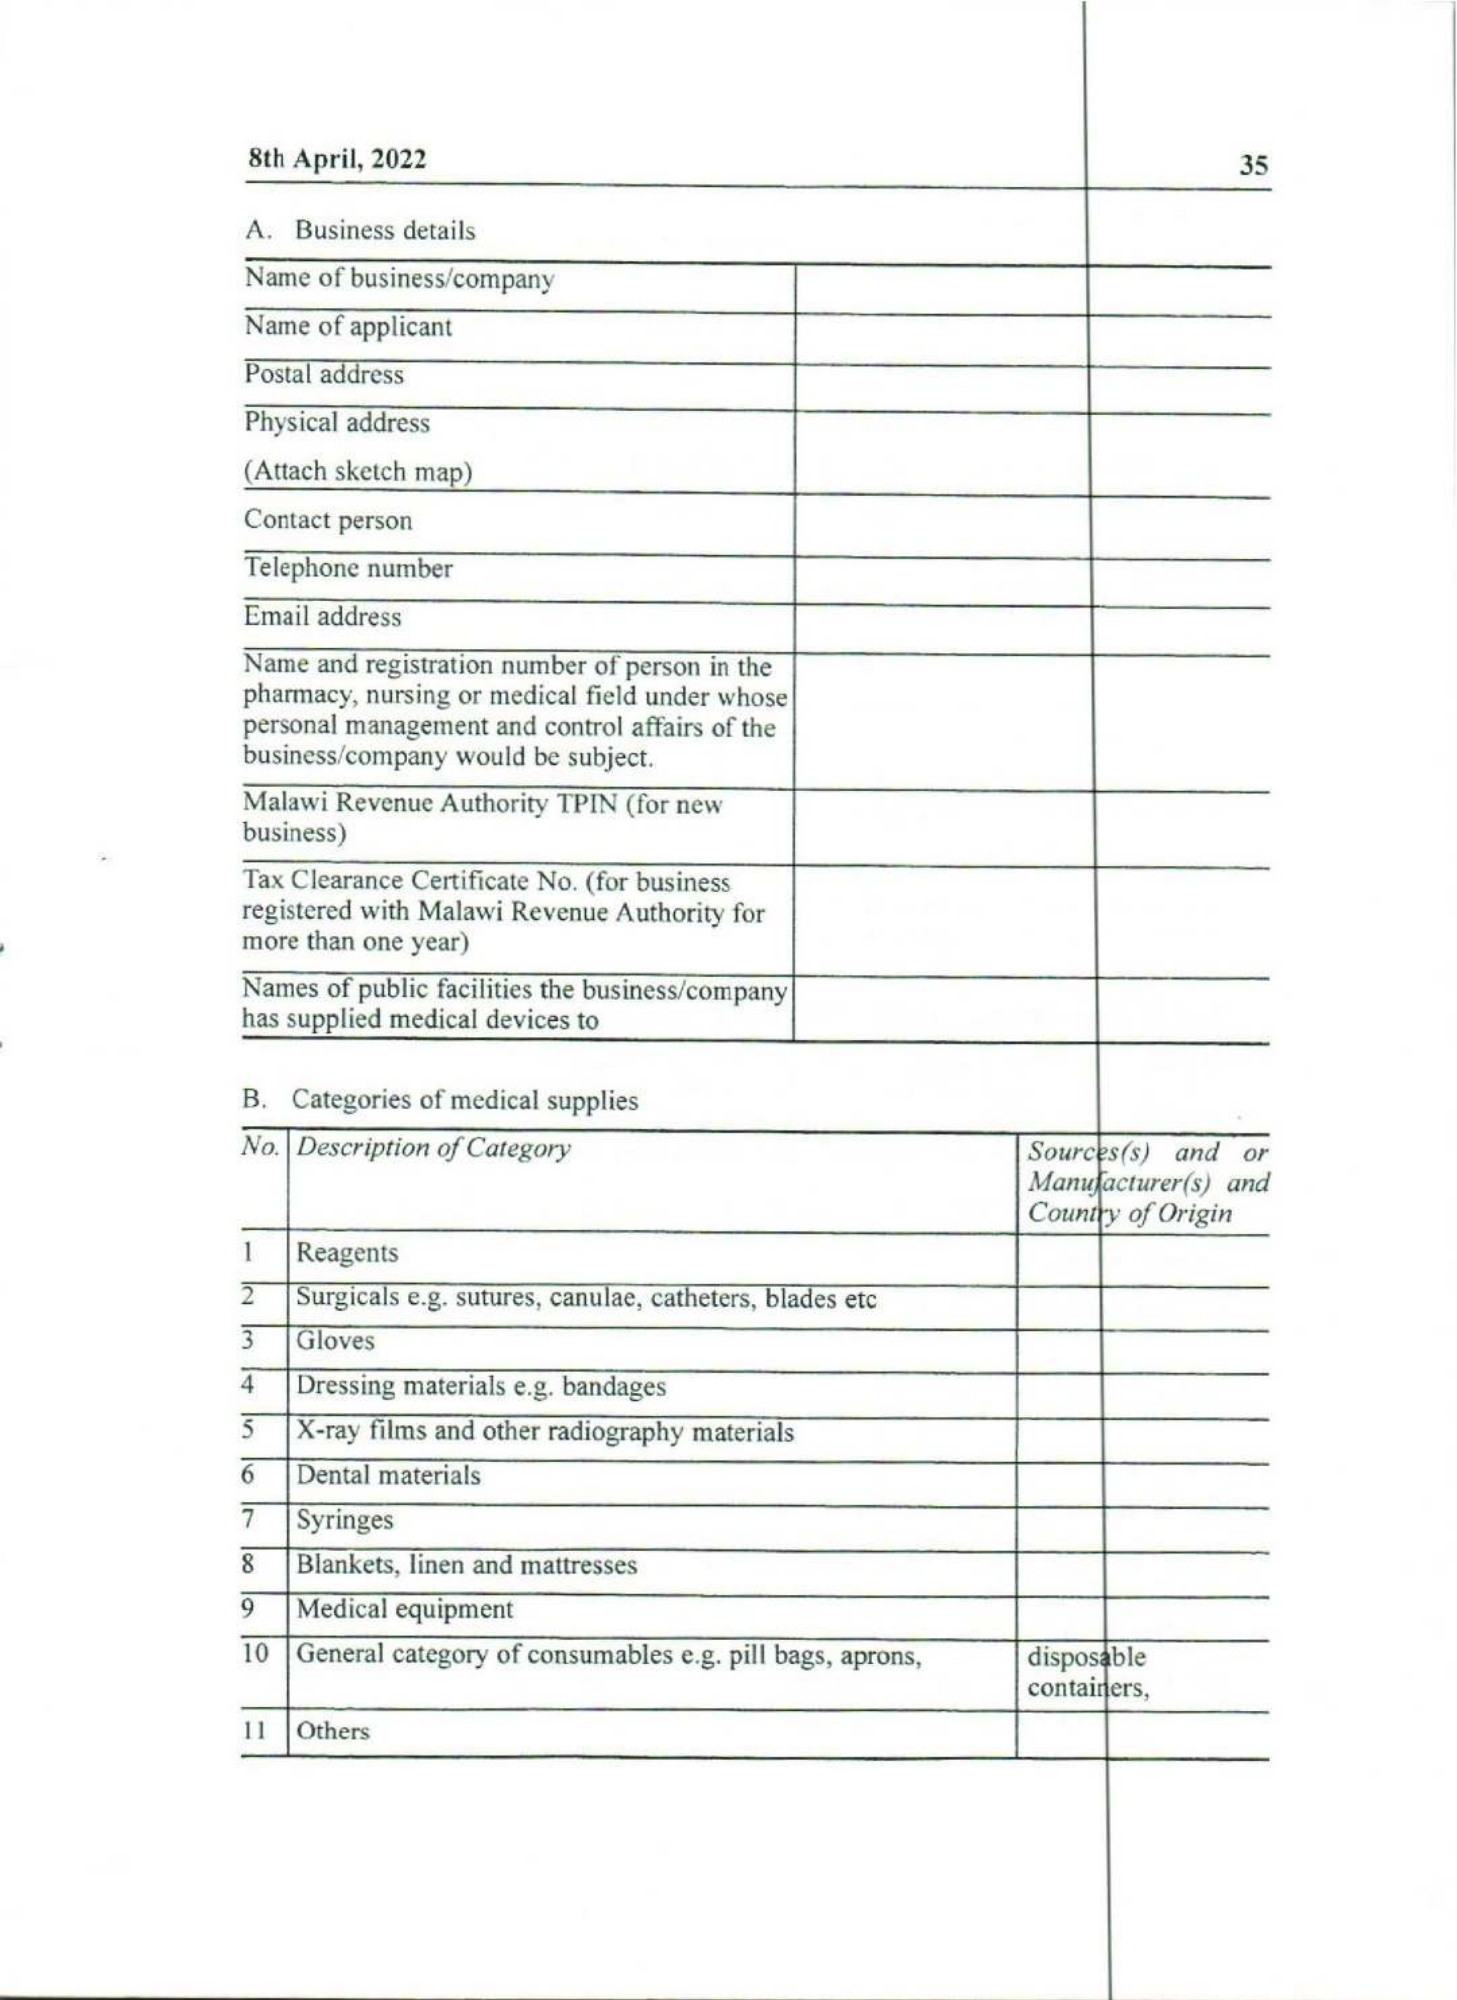
8th April, 2022 35
A. Business details
Name of business/company
Name of applicant
Postal address
Physical address
(Attach sketch map)
Contact person
Telephone number
Email address
Name and registration number of person in the
pharmacy, nursing or medical field under whose
personal management and control affairs of the
business/company would be subject.
Malawi Revenue Authority TPIN (for new
business)
Tax Clearance Certificate No. (for business
registered with Malawi Revenue Authority for
more than one year)
Names of public facilities the business/company
has supplied medical devices to
B. Categories of medical supplies
No. | Description of Category | Sources(s) and or Manufacturer(s) and Country of Origin
1 | Reagents |
2 | Surgicals e.g. sutures, canulae, catheters, blades etc |
3 | Gloves |
4 | Dressing materials e.g. bandages |
5 | X-ray films and other radiography materials |
6 | Dental materials |
7 | Syringes |
8 | Blankets, linen and mattresses |
9 | Medical equipment |
10 | General category of consumables e.g. pill bags, aprons, | disposable containers,
11 | Others |
Government Notice 9 of 2022 — official PDF page 19; original table columns, symbols and diagram connections
36 8th April, 2022
C. Competencies and capacity
No | Description | Applicant to fill in the space provided below
1 | Competencies: |
(i) provide the number, qualifications of employees; and
(ii) Is there any employee with experience in handling health
products?
2 | Capacity: |
(i) describe the storage facilities including ventilation, size, and
security; and
(ii) describe installation, and maintenance arrangements for
medical equipment.
D. General instructions
1. A medical device wholesaler shall provide details of the sources or manufacturers of
medical supplies to be stocked.
2. A medical device wholesaler shall have premises which shall be inspected.
3. A medical device wholesaler shall declare “Manufacturer not known” if at this stage
the manufacturer(s) is indeed not known.
4. A medical device wholesaler shall be required to have manufacturers’ authorizations
from their sources when goods are in stock or being supplied.
5. A medical device wholesaler should have a physical location where goods will be kept.
The goods in storage shall require supporting transaction documents such as invoices,
sales register, receipts, order or import documents etc that will be verified by the
Pharmacy and Medicines Regulatory Authority upon demand at any time.
6. A medical device wholesaler should declare the category or categories of medical
supplies intended for supply that will be matched with competency levels and
capacity declared.
I, the abovementioned applicant, submit herewith a licence application fee of
K........................
Date ........................................ ........................................
Signature of applicant
FOR OFFICE USE ONLY—
(a) Licence application fee of K ..................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of pre mises................................................................
(d) Date of approval of application...............................................................
(e) Licence number ..................................................................................
(f) Receipt number of application .................................................................
Government Notice 9 of 2022 — official PDF page 20; original table columns, symbols and diagram connections
8th July, 2016 37
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 10
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE DISPENSING
BUSINESS IS TO BE CARRIED ON
(Section 52)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of clinic/ hospital......................................................................
2. Registration status (attach copy of registration certificate of the clinic/hospital)
........................................................................................................
3. Postal address..................................................................................
4. Email address: .................................... Telephone number:........................
5. Location of premises on which a medicine store business is to be carried out (city/town,
street, plot no.) (include a sketch map) .........................................................
........................................................................................................
6. Name and registration number of the clinician (attach copy of valid registration
certificate) ...........................................................................................
........................................................................................................
7. Name, qualifications, experience and registration status of dispenser (attach copy of
valid registration certificate)......................................................................
8. I, the abovementioned applicant, submit herewith a licence application fee of K..........
Date ........................................ ........................................
Signature of applicant
Government Notice 9 of 2022 — official PDF page 21; original table columns, symbols and diagram connections
38 8th April, 2022
9. FOR OFFICE USE ONLY—
(a) Licence application fee of K....................................................................
(b) Date of inspection: ..............................................................................
(c) Remarks:...........................................................................................
(d) Receipt number of licence fees: ................................................................
(e) Date of approval..................................................................................
(f) Licence number...................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 11
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE DISPENSING
BUSINESS IS TO BE CARRIED ON
(Section 52)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of clinic/ hospital..........................................................................
2. Registration status (attach copy of registration certificate of the clinic/hospital)
........................................................................................................
3. Postal address......................................................................................
4. Email address: .................................... Telephone number:..........................
5. Previous location of the premises................................................................
6. Location of premises on which a medicine store business is to be carried out (city/town,
street, plot no.) (include a sketch map) .............................................................
........................................................................................................
Government Notice 9 of 2022 — official PDF page 22; original table columns, symbols and diagram connections
8th April, 2022 39
7. Name and registration number of the clinician (attach copy of valid registration
certificate)..............................................................................................
........................................................................................................
8. Name, qualifications, experience and registration status of dispenser (attach copy of
valid registration certificate)........................................................................
9. I, the abovementioned applicant, submit herewith an application fee of K..................
Date ........................................ ........................................
Signature of applicant
10. FOR OFFICE USE ONLY—
(a) Application fee of K..............................................................................
(b) Date of inspection: ..............................................................................
(c) Remarks:...........................................................................................
(d) Receipt number of licencing fees: ..............................................................
(e) Date of approval..................................................................................
(f) Licence number...................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 12
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE VETERINARY SHOP
BUSINESS IS TO BE CARRIED ON
(Section 53)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of applicant..................................................................................
2. Postal address......................................................................................
3. Email address: .................................... Telephone number:..........................
Government Notice 9 of 2022 — official PDF page 23; original table columns, symbols and diagram connections
40 8th April, 2022
4. Location of premises on which the veterinary shop business is to be carried out
(city/town, street, plot no.) (include a sketch map) ................................................
........................................................................................................
5. Name and registration number of the veterinary personnel having control of the
premises referred to in paragraph 4 (attach copy of valid registration certificate)
........................................................................................................
........................................................................................................
6. I, the abovementioned applicant, submit herewith a licence application fee of
K........................
Date ........................................ ........................................
Signature of applicant
7. FOR OFFICE USE ONLY—
(a) Licence application fee of K......................................,...........................
(b) Date of inspection: ..............................................................................
(c) Remarks:...........................................................................................
(d) Receipt number of licence fees: ................................................................
(e) Date of approval..................................................................................
(f) Licence number...................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 13
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE VETERINARY
SHOP BUSINESS IS TO BE CARRIED ON
(Section 53)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of applicant..................................................................................
Government Notice 9 of 2022 — official PDF page 24; original table columns, symbols and diagram connections
8th April, 2022 41
2. Postal address......................................................................................
3. Email address ........................................ Telephone number........................
4. Previous location of the wholesale pharmacy.....................................................
........................................................................................................
5. Location of premises on which the veterinary shop business is to be carried out
(city/town, street, plot no.) (include a sketch map) ................................................
........................................................................................................
6. Name and registration number of the veterinary personnel having control of the
premises referred to in paragraph 5 (attach copy of valid registration certificate)
........................................................................................................
........................................................................................................
7. I, the abovementioned applicant, submit herewith an application fee of
K............................
Date ........................................ ........................................
Signature of applicant
8. FOR OFFICE USE ONLY—
(a) Application fee of K..............................................................................
(b) Date of inspection: ..............................................................................
(c) Remarks:...........................................................................................
(d) Receipt number of licence fees: ................................................................
(e) Date of approval..................................................................................
(f) Licence number...................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 14
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE A MEDICINE STORE
BUSINESS IS TO BE CARRIED ON
(Section 41)
Government Notice 9 of 2022 — official PDF page 25; original table columns, symbols and diagram connections
42 8th April, 2022
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of applicant..................................................................................
2. Email address........................................ Telephone number........................
3. Postal address......................................................................................
4. Location of premises on which a medicine store business is to be carried out (city/town,
street, plot no.) (include a sketch map)..............................................................
5. Where the applicant is a company—
(a) state the registration number of company under the Act: ....................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of the certificate of incorporation of the company
........................................................................................................
........................................................................................................
6. Name and registration number of a full-time pharmacy personnel having control of the
premises referred to in paragraph 4
........................................................................................................
........................................................................................................
7. I, the abovementioned applicant, submit herewith licencing application fee of K..........
Date ........................................ ........................................
Signature of applicant
8. FOR OFFICE USE ONLY—
(a) Licence application fee of K ....................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Licence number ..................................................................................
(f) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
Government Notice 9 of 2022 — official PDF page 26; original table columns, symbols and diagram connections
8th April, 2022 43
[*1. Fee is payable only by cash or cheque.
2. Application fee is not refundable.]
Form No. 15
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE A MEDICINE
STORE BUSINESS IS TO BE CARRIED ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of applicant..................................................................................
2. Email address........................................Telephone number..........................
3. Previous location of medicine store.................................................................
4. Postal address......................................................................................
5. Location of premises on which a medicine store business is to be carried out (city/town,
street, plot no.) (include a sketch map)..............................................................
6. Where the applicant is a company—
(a) state the registration number of company under the Act: ....................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of the certificate of incorporation of the company
........................................................................................................
........................................................................................................
7. Name and registration number of a full-time pharmacy personnel having control of the
premises referred to in paragraph 5..................................................................
........................................................................................................
8. I, the abovementioned applicant, submit herewith an application fee of
K............................
Date ........................................ ........................................
Signature of applicant
Government Notice 9 of 2022 — official PDF page 27; original table columns, symbols and diagram connections
44 8th April, 2022
9. FOR OFFICE USE ONLY—
(a) Application fee of K ..............................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Licence number ..................................................................................
(f) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 16
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE CURRENT GOOD
MANUFACTURING PRACTICE INSPECTION BUSINESS IS TO BE CARRIED
ON
(Section 41)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Particulars of applicant—
(a) Name of applicant................................................................................
(b) Physical address...................................................................................
(c) Country............................................................................................
(d) Phone number....................................Telefax........................................
Email address.........................................................................................
2. Particulars of site to be inspected—
(a) Name of site.......................................................................................
(b) Physical address...................................................................................
Government Notice 9 of 2022 — official PDF page 28; original table columns, symbols and diagram connections
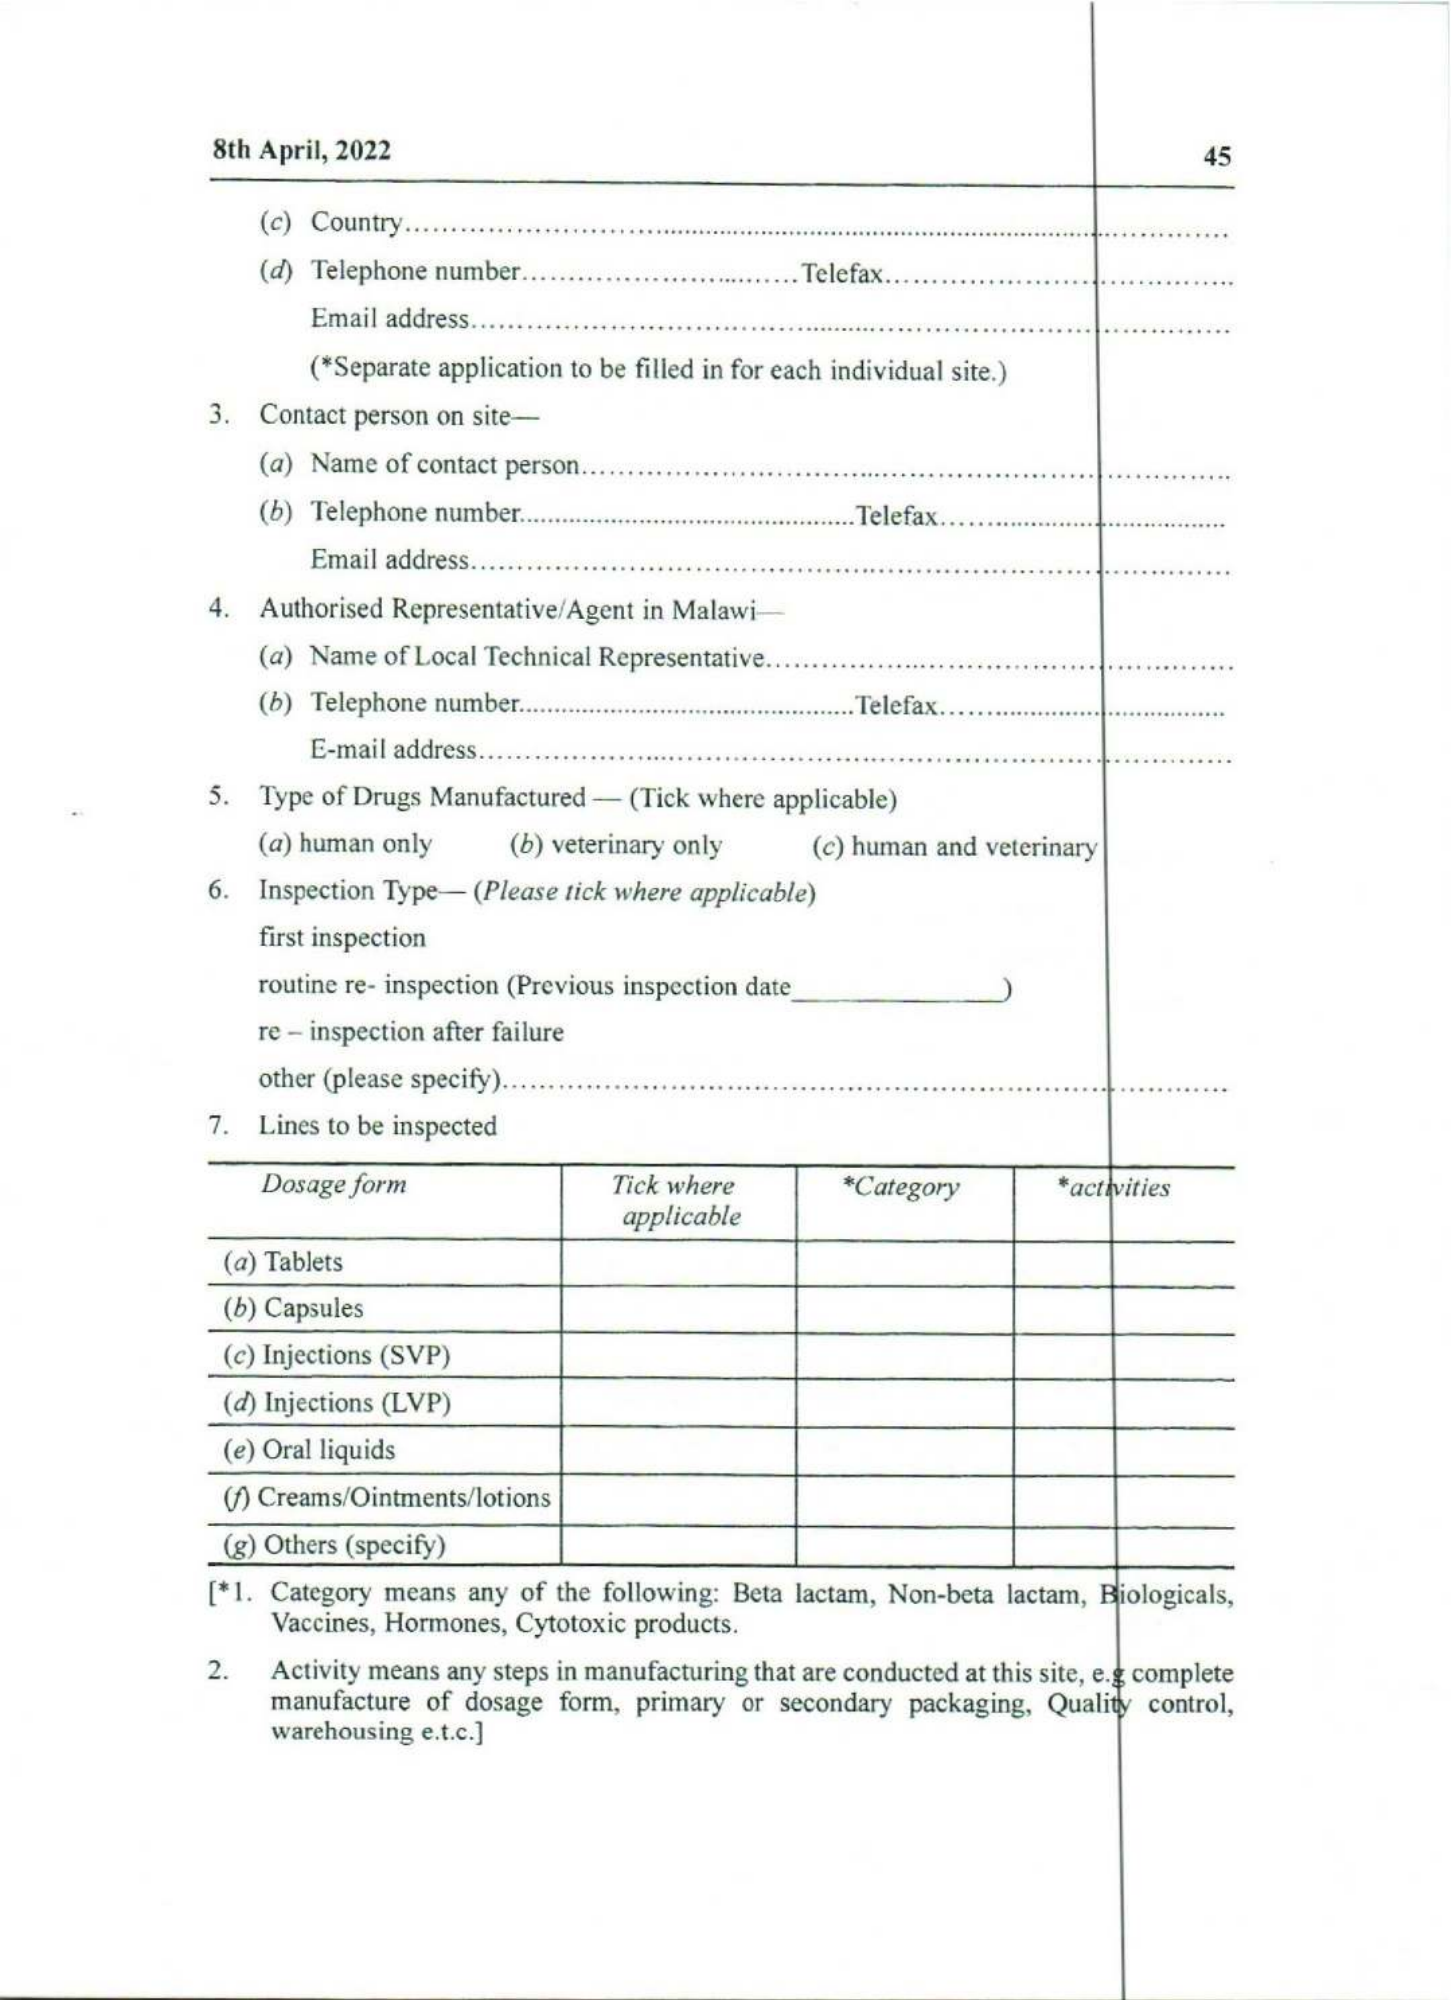
8th April, 2022 45
(c) Country............................................................................................
(d) Telephone number................................Telefax........................................
Email address.........................................................................................
(*Separate application to be filled in for each individual site.)
3. Contact person on site—
(a) Name of contact person..........................................................................
(b) Telephone number................................Telefax........................................
Email address.........................................................................................
4. Authorised Representative/Agent in Malawi—
(a) Name of Local Technical Representative.......................................................
(b) Telephone number................................Telefax........................................
E-mail address.........................................................................................
5. Type of Drugs Manufactured — (Tick where applicable)
(a) human only (b) veterinary only (c) human and veterinary
6. Inspection Type— (Please tick where applicable)
first inspection
routine re- inspection (Previous inspection date________________)
re – inspection after failure
other (please specify).................................................................................
7. Lines to be inspected
Dosage form | Tick where applicable | *Category | *activities
(a) Tablets | | |
(b) Capsules | | |
(c) Injections (SVP) | | |
(d) Injections (LVP) | | |
(e) Oral liquids | | |
(f) Creams/Ointments/lotions | | |
(g) Others (specify) | | |
[*1. Category means any of the following: Beta lactam, Non-beta lactam, Biologicals,
Vaccines, Hormones, Cytotoxic products.
2. Activity means any steps in manufacturing that are conducted at this site, e.g complete
manufacture of dosage form, primary or secondary packaging, Quality control,
warehousing e.t.c.]
Government Notice 9 of 2022 — official PDF page 29; original table columns, symbols and diagram connections
46 8th April, 2022
8. Registration of Products—
(a) Have you submitted dossier for registration? Yes No
(b) If Yes, list the products applicable. (Attach a separate sheet)
........................................................................................................
9. Site Master File
Please attach copy of the Site Master File (not more than 25 pages).
Enclosed - Yes No
I hereby certify that the above information is correct and apply for Good Manufacturing
Practice inspection of the above-named site.
Date ........................................ ........................................
Signature of applicant
FOR OFFICE USE ONLY—
(a) Date of inspection.................................................................................
(b) Remarks...........................................................................................
(c) Receipt of cGMP fees.............................................................................
(d) Date of approval..................................................................................
(e) Licence number...................................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 17
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF PREMISES WHERE PHARMACEUTICAL
MANUFACTURING BUSINESS IS TO BE CARRIED ON
(Section 57)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of business..................................................................................
Government Notice 9 of 2022 — official PDF page 30; original table columns, symbols and diagram connections
8th April, 2022 47
2. Name of applicant..................................................................................
3. Postal address......................................................................................
4. Email address........................................ Phone number ............................
5. Location of premises on which wholesale pharmacy business is re-located (city/town,
street, plot no.) (include a sketch map)
........................................................................................................
........................................................................................................
6. Where the applicant is a company—
(a) state the registration number of company under the Act......................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of certificate of incorporation of the company
........................................................................................................
........................................................................................................
7. Name and registration number of supervising pharmacist having control of the
premises referred to in paragraph 5
........................................................................................................
........................................................................................................
8. Competent technical staff—
(a) Production pharmacist............................................................................
(b) Quality control analyst...........................................................................
9. I, the abovementioned applicant, submit herewith an licencing application fee of
K........................
Date ........................................ ........................................
Signature of applicant
10. FOR OFFICE USE ONLY—
(a) Licence application fee of K......................................................................
(b) Remarks...........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Registration number ..............................................................................
(f) Receipt number of application ..................................................................
Government Notice 9 of 2022 — official PDF page 31; original table columns, symbols and diagram connections
48 8th April, 2022
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 18
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR LICENCING OF NEW PREMISES WHERE
PHARMACEUTICAL MANUFACTURING BUSINESS IS TO BE CARRIED ON
(Section 57)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Name of business..................................................................................
2. Name of applicant..................................................................................
3. Postal address......................................................................................
4. Email address........................................_ Phone number ............................
5. Previous location of the manufacturer.............................................................
6. Location of premises on which wholesale pharmacy business is re-located (city/town,
street, plot no.) (include a sketch map)
........................................................................................................
........................................................................................................
7. Where the applicant is a company—
(a) state the registration number of company under the Act......................................
(b) state the name and registration number of the person under whose personal
management and control affairs of the company would be subject to
........................................................................................................
........................................................................................................
(c) attach a copy of certificate of incorporation of the company
........................................................................................................
........................................................................................................
Government Notice 9 of 2022 — official PDF page 32; original table columns, symbols and diagram connections
8th April, 2022 49
8. Name and registration number of supervising pharmacist having control of the
premises referred to in paragraph 6..................................................................
........................................................................................................
........................................................................................................
9. Competent technical staff—
(a) Production pharmacist............................................................................
(b) Quality control analyst...........................................................................
10. I, the abovementioned applicant, submit herewith an application fee of K ..................
Date ........................................ ........................................
Signature of applicant
11. FOR OFFICE USE ONLY—
(a) Application fee of K ..............................................................................
(b) Remarks...........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Registration number ..............................................................................
(f) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 19
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
CERTIFICATE OF LICENCING OF PREMISES WHERE A *RETAIL
PHARMACY OR WHOLESALE PHARMACY BUSINESS OR MEDICINE
STORE OR DISPENSING OR VETERINARY OR PHARMACEUTICAL
MANUFACTURING BUSINESS IS TO BE CARRIED ON
(Sections 42, 52, 53 and 57)
Registration number ............................ Certificate number ................................
This is to certify that the premises situated at ....................................................
(state location of premises, namely town, street and plot no.)
Government Notice 9 of 2022 — official PDF page 33; original table columns, symbols and diagram connections
50 8th April, 2022
where .................................................................... is authorized to carry out a
(Name of business owner)
*retail pharmacy business or wholesale pharmacy business or dispensing facility or
veterinary shop business or medicine store or pharmaceutical manufacturer, on this
........................................ day of ........................................, 20 ..........
registered on the register of premises where the business is to be carried on, kept and
maintained by the Pharmacy and Medicines Regulatory Authority in accordance with the
provisions of the Pharmacy and Medicines Regulatory Authority Act and the Regulations
made thereunder.
Date ........................................
.................................... ....................................
Director General Chairperson
Common Seal
(*Delete whichever is not applicable)
Form No. 20
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
REGISTER OF PHARMACY PRACTICE PREMISES
(Section 54)
Location of registered premises | | | Date of registration | Registration | Name, registration and certificate number of registration pharmacist in control of business | Remarks, if any
Town | Street | Plot No. | | | |
Government Notice 9 of 2022 — official PDF page 34; original table columns, symbols and diagram connections
8th April, 2022 51
Form No. 21
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR AUTHORIZATION FOR THE MARKETING, ADVERTISING
OF MEDICINES OR ALLIED SUBSTANCES
(Section 62)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. Particulars of applicant—
(a) Name of applicant ...............................................................................
(b) Physical address/location........................................................................
(c) Postal address.....................................................................................
(d) Email address.....................................................................................
2. Description of Advertisement—
(a) Type of activity for which application is made
........................................................................................................
(b) Type of material (s) to be used (Attach two samples)
........................................................................................................
(c) Medicine or allied substance name...............................................................
(d) Language of the publication or advert............................................................
(e) Intended target group.............................................................................
Date ........................................ ........................................
Signature of applicant
3. FOR OFFICIAL USE ONLY—
(a) Application fee of K..............................................................................
(b) Receipt number...................................................................................
(c) Date of approval of application..................................................................
(d) Authority’s entry Number........................................................................
(e) Application and samples received................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
Government Notice 9 of 2022 — official PDF page 35; original table columns, symbols and diagram connections
52 8th April, 2022
[*1. Fee is payable only by cash or cheque.
2 Application fee is not refundable.]
Form No. 22
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR AUTHORIZATION FOR DISPOSAL OF UNFIT PRODUCTS
(Sections 69 and 129)
To: The Director General
Pharmacy and Medicines Regulatory Authority
P.O. Box 30241
Lilongwe 3
1. I/We................................................................................................
of ......................................................................................................
(postal address)
undertaking the business of .................................................... hereby apply
for disposal of unfit ...................................................................................
(type of products)
2. Location of business (include a sketch map) .....................................................
3. Name of supervising pharmacist of the premises..................................................
4. Registration number (if applicable)................................................................
5. Reason for disposal..................................................................................
........................................................................................................
6. Estimated value of unfit products, K.................................................................
7. Attached herewith is the list of products to be disposed of (Attach Health Products
Disposal Log)
........................................................................................................
8. Declaration:
I certify that the information provided in the application form is true and correct.
Date ........................................ ........................................
Signature of applicant
Government Notice 9 of 2022 — official PDF page 36; original table columns, symbols and diagram connections
8th April, 2022 53
9. FOR OFFICE USE ONLY—
(a) Application fee of K ..............................................................................
(b) Remarks ..........................................................................................
(c) Date of inspection of premises..................................................................
(d) Date of approval of application..................................................................
(e) Receipt number of application ..................................................................
Date ........................................ ........................................
Director General
Pharmacy and Medicines Regulatory Authority
[*1. Fee is payable only by cash or cheque.
2 Application fees are not refundable.]
Form No. 23
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
APPLICATION FOR PRODUCT LICENCE (SUMMARY SHEET)
(Sections 62(1))
A. Product Identification
1. PMRA Ref No. | 2. Proprietary name | 3. Non-proprietary name (INN)
(for office use only) | |
4.Dosage form and colour | 5. Strength | 6. Route of administration
7. Suggested Price (Optional) | |
B. Applicant details
1. Name of applicant
2. Address of Applicant (including contact person) | 3. City/town | 4. County
5. Telephone No. | 6. Fax No. | 7. Telex | 8. Email address
Government Notice 9 of 2022 — official PDF page 37; original table columns, symbols and diagram connections
54 8th April, 2022
C. Manufacturer details
1. Name of manufacturer | 2. Address
3. City/town | 4. Country | 9. Manufacturing Licence No. (attach copies of certificates) | 10. Licence date
5. Telephone No. | 6. Fax No. | 11. Name and address of licensing authority
7. Telex No. | 8. Email address | 12.Date of Last GMP inspection. Attach copies of certificates issued by both local NRA and PMRA
D. Product details
1. Therapeutic category | 2.Main indication(s)
3. Dosage details and method of use | 4.Stability data (on three consecutive production batches.
Provide detailed studies and results (attach validation
reports for analytical tests methods used). The stability
studies should be conducted in line with Zone IVA or
IVB for products meant for storage under prevailing
environmental conditions.)
5. Shelf life | 6.Storage conditions (supported by the stability data)
7. Complete quantitative formula (per dose form)
(a) Substance | (b) Function | (c) Amount | (d) QC specifications
(i) | | |
(ii) | | |
Government Notice 9 of 2022 — official PDF page 38; original table columns, symbols and diagram connections
8th April, 2022 55
(a) Substance | (b) Function | (c) Amount | (d) QC specifications
(iii) | | |
(iv) | | |
(v) | | |
(vi) | | |
(vii) | | |
(viii) | | |
| | 8. Total weight or volume of dose form |
Government Notice 9 of 2022 — official PDF page 39; original table columns, symbols and diagram connections
56 8th April, 2022
1. Therapeutic category | 2. Main indication(s)
3. Dosage details and method of use | 4. Stability data (on first three batches)
5. Shelf life | 6. Storage conditions.
E. Active ingredient details
9. Active ingredients
(a) Active ingredient name | (b) Source of active ingredient | (c)Standard e.g. USP, BPcontrols | (d) In- process (optional)
(i) | | |
(ii) | | |
(iii) | | |
(iv) | | |
Government Notice 9 of 2022 — official PDF page 40; original table columns, symbols and diagram connections
8th April, 2022 57
F. Chemistry, Manufacturing and Control of Active Pharmaceutical Ingredient
Active pharmaceutical ingredient | Detailed validated method of synthesis of active pharmaceutical ingredient | In process controls for critical quality attributes including particle size distribution: (d10, d50, d90), polymorphism and isomerism | Solubility at pH 1.2, 4.5 or 6.8
| | |
| | |
| | |
G. Manufacturing and Quality Control information
1. Method of manufacture of dosage form (attach flow diagrams and validation reports for
manufacturing processes)
2. In process control details (sampling stages and validated test methods used, attach
validation reports for analytical tests used)
3. Quality control specifications of the final product (attach as annex)
4. Details of the validated method of analysis for the final product (attach analytical
validation reports)
Government Notice 9 of 2022 — official PDF page 41; original table columns, symbols and diagram connections
58 8th April, 2022
5. Batch No. | 6. Date of Manufacture | 7. Expiry date
8. Executed and Blank Batch Manufacturing Records. Results of batch testing (Certificate
of Analysis including that for biobatch or batch used for dissolution profile). Validation
reports for analytical tests should be provided as an annex.
9. Certificate of Pharmaceutical Product in line with WHO format
10. Free Sale Certificate
H. Bio-equivalence Data
Detailed study of comparative bioavailability, with pharmacokinetics data; include study
protocols, results and conclusions of study demonstrating bio-equivalence for BCS class II
and IV active pharmaceutical ingredients. Attach copies of ethical approval, curriculum
vitae of PI, certificate of accreditation of Contract Clinical Research Organization, reports
of validated analytical test methods used for QC analysis of pharmacokinetic data. Submit
comparative dissolution data for BSC class I and III active pharmaceutical ingredients.
I. Container information
(a) Size of container (number of unit doses) | (b) Description of container closure system including nature of materials and art work.
(i) |
(ii) |
(iii) |
Government Notice 9 of 2022 — official PDF page 42; original table columns, symbols and diagram connections
8th April, 2022 59
J. Distribution and Promotional information
1. What is the intended scheduling status of the product? (tick appropriate box)
(a) CD Controlled drug | (b) POM Prescription only medicine | (c) PIM Pharmacist initiated medicine | (d) P Pharmacy only medicine | (e) GSL General Sales List medicine | (f) Veterinary use only medicine
2. How is it proposed to promote the medicinal product? (tick appropriate box)
(a) to the medical and pharmacy professions only
(b) to the general public by point of sale displays in pharmacies
(c) to the general public
(d) other (please specify)
K. Current Regulatory status of product in other countries (attach relevant supporting
documents)
(a) Country | (b) Product Licence Number. | (c) Date of First Registration
(i) | |
(ii) | |
(iii) | |
(iv) | |
(v) | |
Government Notice 9 of 2022 — official PDF page 43; original table columns, symbols and diagram connections
60 8th April, 2022
L. Date and Signature of authorised person (s)
(a) Date of application | (b) Signature of Authorized person e.g. Pharmacist
(c) Applicant’s official seal |
M. Registration Information (for office use only)
(a) Application fee | (b)Application fee receipt number. | (c) Registration fee | (d)Registration fee receipt number.
(e) Registration date | (f) Registration expiry date | (g) Registration number |
(h) Full name and signature
Director General
Pharmacy and Medicines Regulatory Authority
Form No. 24
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(NO. 9 OF 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
PRODUCT LICENCE
(Section 62(8))
Product Licence Number .................... issued at ................................................
under section 62 of the Pharmacy and Medicines Regulatory Authority Act to
........................................................................................................
(name of person or firm to whom licence is issued)
of ......................................................................................................
(state city, street, plot number and postal address)
Government Notice 9 of 2022 — official PDF page 44; original table columns, symbols and diagram connections
8th April, 2022 61
who is hereby licensed to engage in any or all of the business activities outlined under
section 41 of, and subject to, the Act in regard to the following medicinal product(s) in
accordance with the special conditions specified hereunder—
(a) Medicinal product identity—
(i) name ...............................................................................................
(ii) generic form ......................................................................................
(iii)dosage form .......................................................................................
(iv) strength ...........................................................................................
(v) manufacturing .....................................................................................
(vi) manufacturing country ..........................................................................
(b) Year and therapeutic category of the medicinal product
(c) Scheduling status
(d) Declaration of content—
(i) active ingredient ..................................................................................
(ii) content per unit dose .............................................................................
(e) Package—
(i) type of package ....................................................................................
(ii) size of package ....................................................................................
(iii)initial retail price per package ...................................................................
Further conditions of this Product Licence are—
Valid until ........................................, 20 ..........
Date ............................................................
.................................... ....................................
Director General Chairperson
Common Seal
Form No. 25
PHARMACY AND MEDICINES REGULATORY AUTHORITY ACT
(No. 9 of 2019)
PHARMACY AND MEDICINES REGULATORY AUTHORITY (FEES AND
FORMS) REGULATIONS
REGISTER OF PRODUCT LICENCES
(section 71)
Government Notice 9 of 2022 — official PDF page 45; original table columns, symbols and diagram connections
62 8th April, 2022
Product licence | | Description of medical products to which licence relates | Name and address of licence holder
No. | Date issued | |
Made this 8th day of April, 2022.
(FILE NO. HTSS-PHARM/1)
K. K. CHIPONDA
Minister of Health
Printed by THE GOVERNMENT PRINTER. Lilongwe, Malawi—(Price K3,645.00)
Government Notice 9 of 2022 — official PDF page 46; original table columns, symbols and diagram connections